
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
The unconscious (comatose) patient
Quick facts | emergency priorities
Clinical summary: This entry requires a disease-specific recognition, red-flag and emergency-management review. Refer to the underlying article and current local pathway; do not use this panel as a treatment protocol.
Browse the Neurology & Stroke textbook: Neurology: Emergencies (specialty landing page only; no disease-level match confirmed)
References: Existing source link (not yet checked)
Editorial draft: the full historic text, doses, and pathways have not been clinically signed off. Cross-check BNF/BNFC and local protocols.
Related Subjects: |Assessing Coma and Management |Glasgow Coma scale |Acute Poisoning |Trauma: Traumatic Brain Head Injury (TBI) |Acute Anaphylaxis |Basic Life Support |Advanced Life Support |Acute Stroke Assessment |Brain Herniation syndromes |Haemorrhagic stroke |Acutely ill patient |Distributive Shock |Hypovolaemic or Haemorrhagic Shock |Obstructive Shock |Septic Shock and Sepsis |Shock (General Assessment)
⚠️ If the cause of coma is uncertain (e.g. CT negative), always consider giving the CAND bundle: 💉 Cefotaxime (meningitis cover), 💊 Aciclovir (HSV encephalitis), 💉 Naloxone (opiates), 🍬 Dextrose ± Pabrinex (thiamine, prevent Wernicke’s). This covers the major reversible causes until further information is available.
| 🛠️ Coma Management Overview |
|---|
|
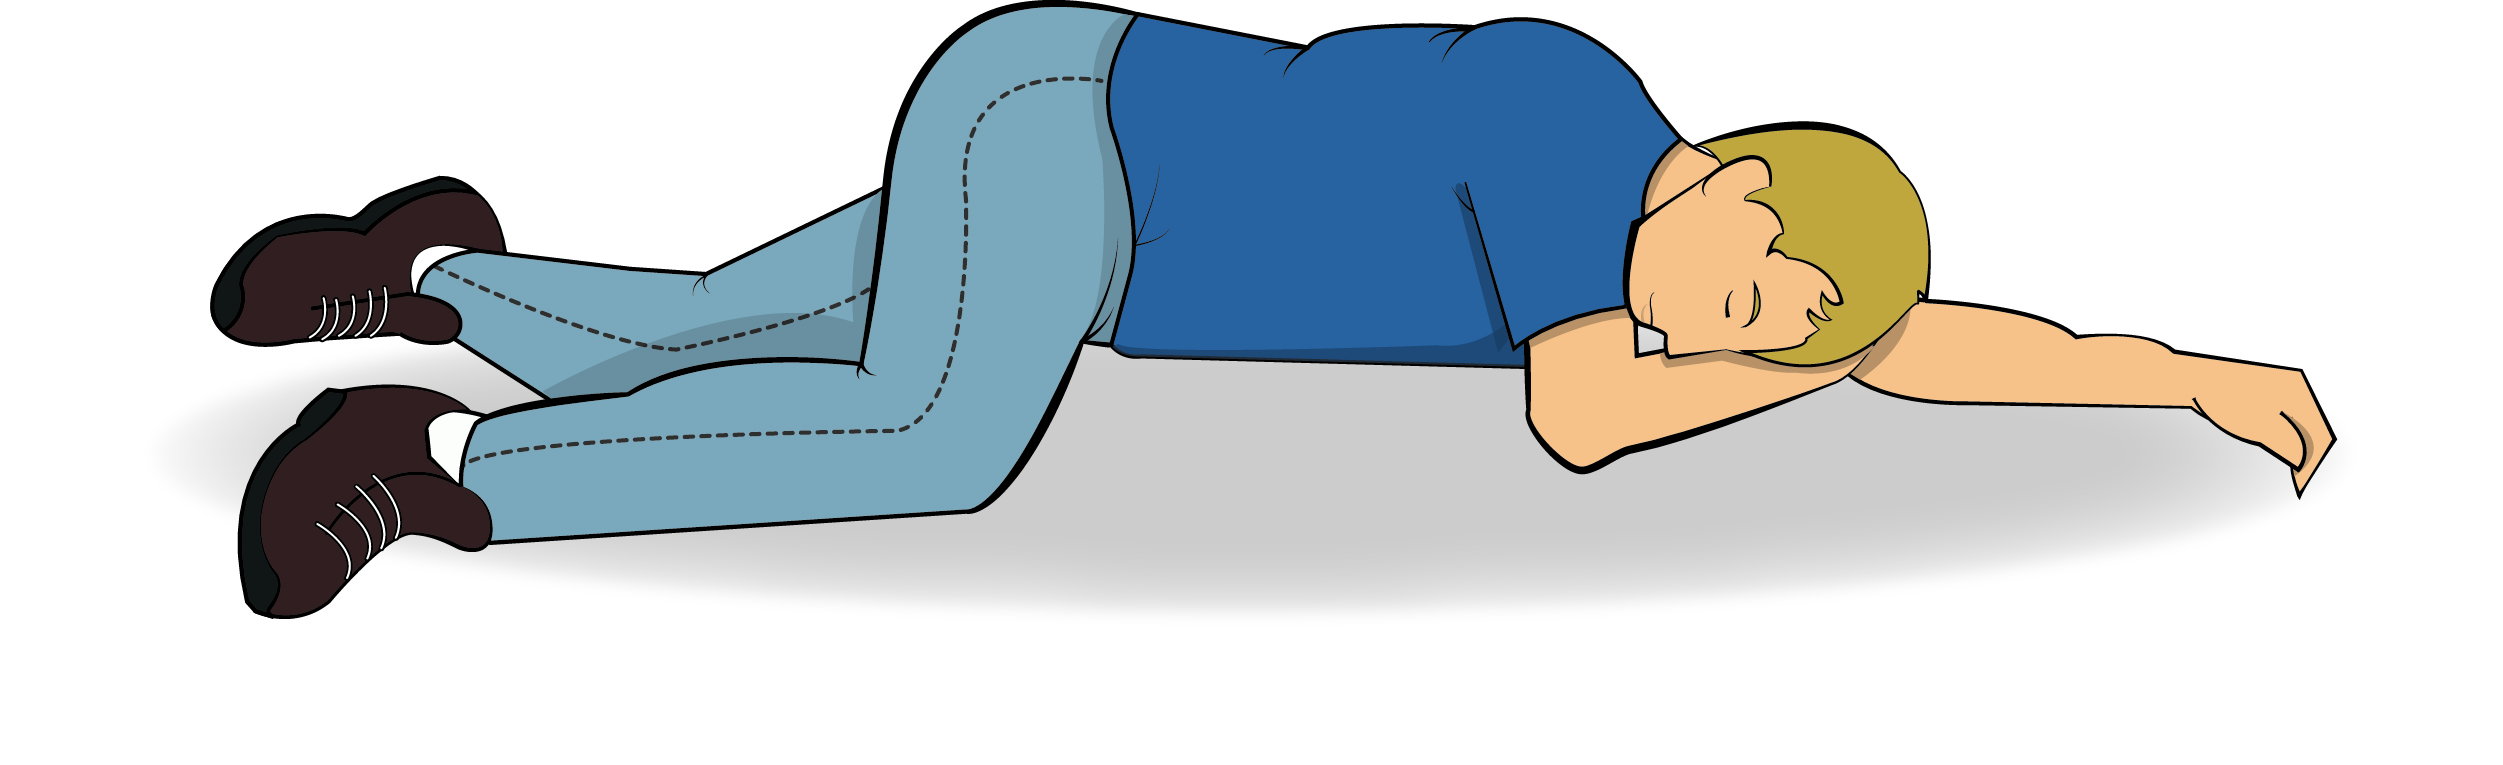
🛌 Recovery Position
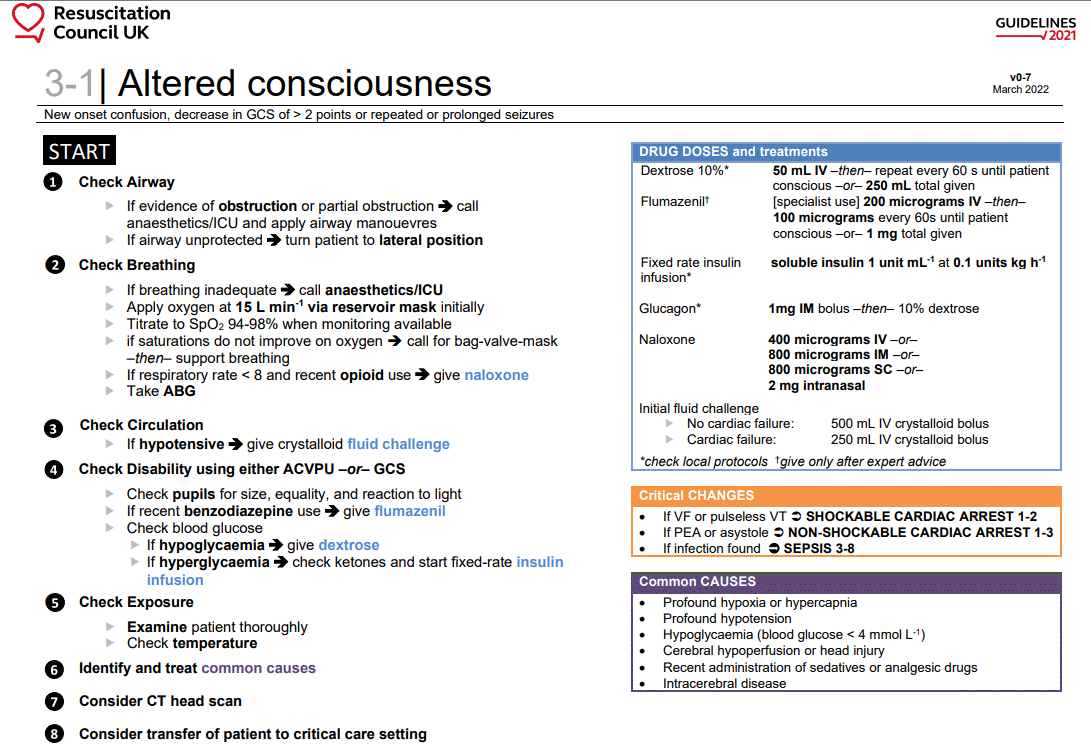
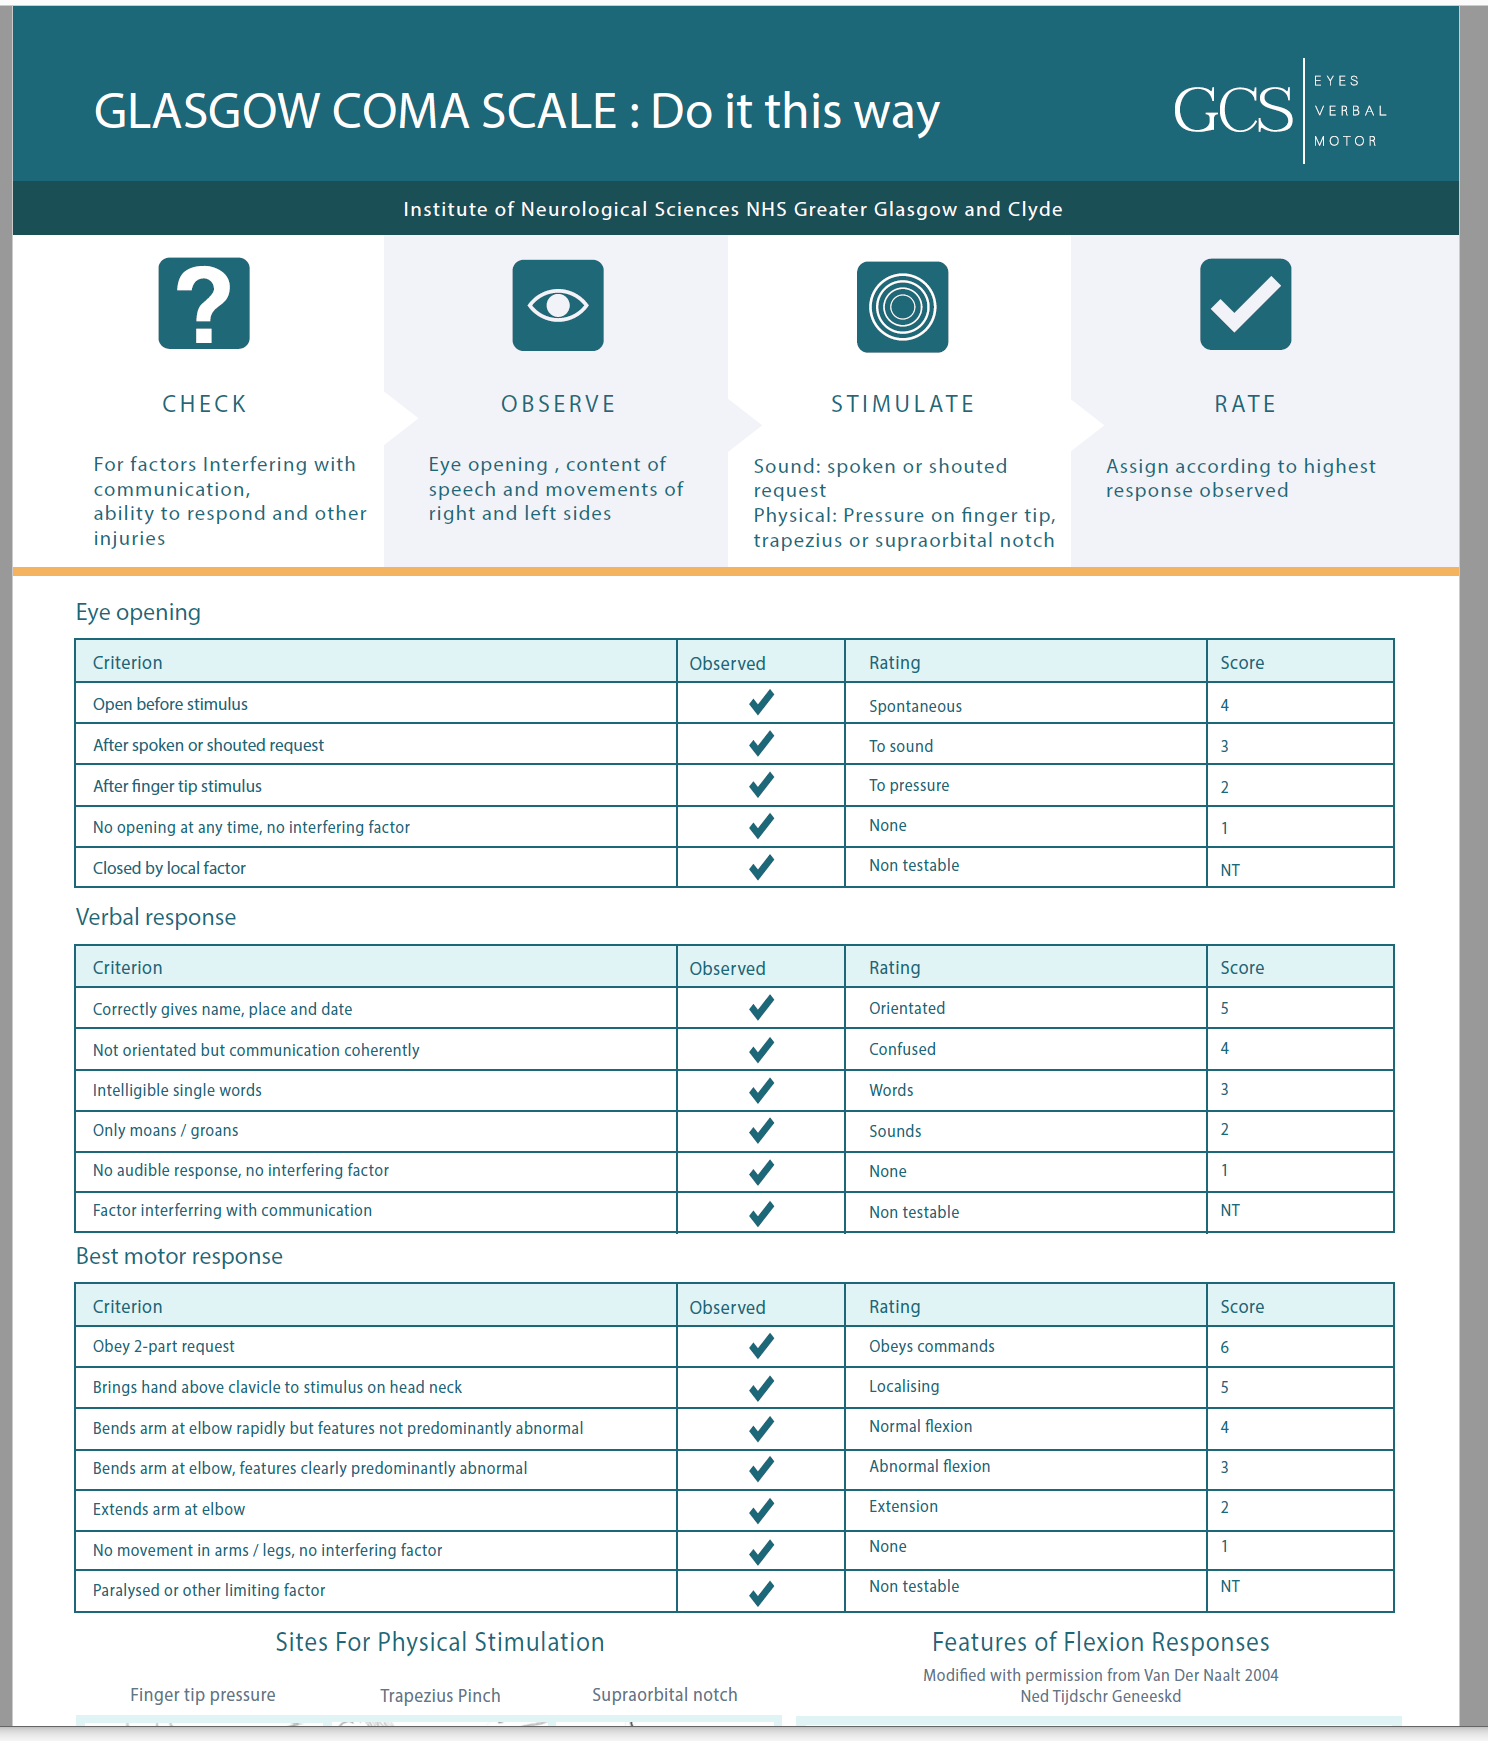
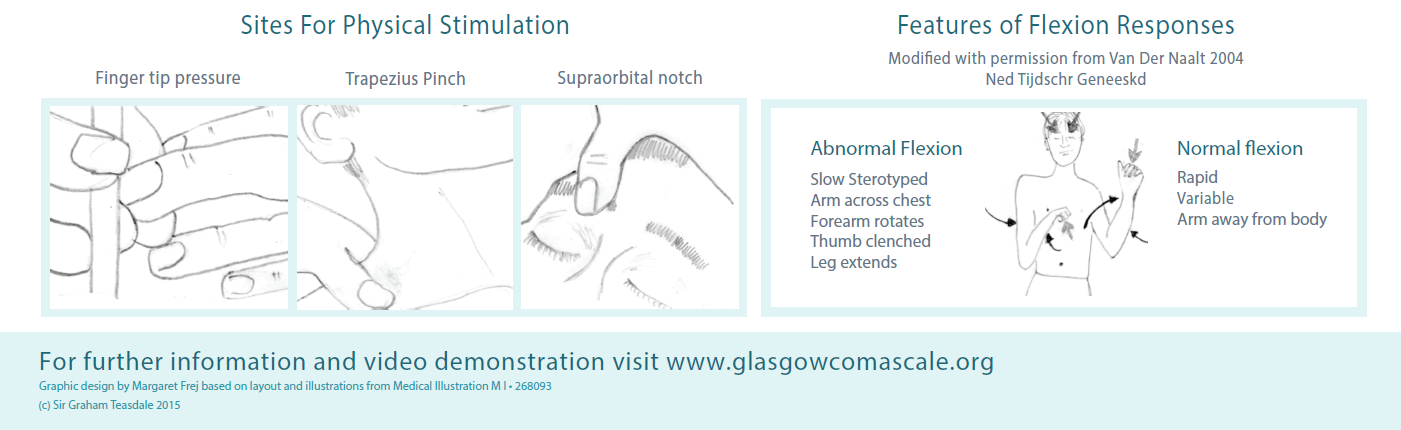
📏 Assessment of Coma: GCS & Pupils
🧠 Pathophysiology of Coma (ARAS)
- Consciousness requires intact Ascending Reticular Activating System (ARAS) + cortex.
- ARAS = brainstem nuclei → thalamus → cortex.
- Coma occurs with ↑ ICP, bilateral cortical/thalamic damage, or brainstem dysfunction.
- Pupils give localising clues: 🔴 Bilateral dilated, fixed → herniation/brainstem failure. 🔵 Pinpoint → pons or opioids. ⚖️ Unequal → structural lesion compressing CN III.
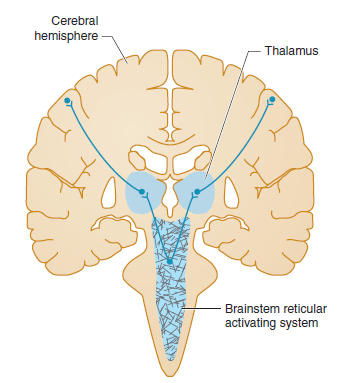
🧩 Consciousness depends on ARAS (midbrain/pons) + both cerebral hemispheres. Structural lesions or diffuse metabolic insults can both produce coma.
🧪 Differential Diagnosis: CT & Glucose First
| Cause | Clues | Management |
|---|---|---|
| 🍬 Hypoglycaemia | Low CBG | IV Dextrose |
| 💊 Opiate toxicity | Pinpoint pupils | IV Naloxone |
| 🧠 Stroke | Focal neurology | CT head, stroke pathway |
| ⚡ Post-ictal | History of seizure | Recovery position, treat status |
| 🦠 Meningitis/Encephalitis | Fever, neck stiffness | Cefotaxime + Aciclovir |
| ☠️ CO poisoning | Exposure, headache, cherry-red skin | 100% O₂ ± hyperbaric |
| 🤕 Head injury | History of trauma | CT head/C-spine |
| 💧 Hyponatraemia | Na <115, seizures | Hypertonic saline |
| 🧬 Sepsis | Fever, shock | IV Tazocin + Gentamicin |
| 📟 NCSE | Unresponsive, subtle eye movements | EEG, Lorazepam |
| 💥 SDH/EDH | Head trauma | Neurosurgery + Mannitol |
| 🦟 Cerebral malaria | Travel history | IV Quinine |
⚡ Pupils in Coma
| Pupil Type | Description | Causes |
|---|---|---|
| Normal | 3–4 mm, reactive | Metabolic causes |
| Thalamic | ~2 mm, reactive | Thalamic compression |
| Fixed dilated | >7 mm, unreactive | Herniation, CN III compression |
| Midsized fixed | ~5 mm, unreactive | Midbrain lesion |
| Pinpoint | 1–1.5 mm, minimal reaction | Pons, opioids, organophosphates |
| Asymmetric | Anisocoria | Structural lesion, CN III palsy |
🚨 Signs of Trauma
- 🐼 Raccoon eyes (periorbital bruising).
- 🎧 Battle’s sign (mastoid bruising).
- 🩸 Haemotympanum.
- 💧 CSF rhinorrhoea/otorrhoea (confirm with β-2 transferrin).
- 👆 Palpable depressed skull fracture.
📊 Pathophysiologic Patterns
| Feature | Supratentorial | Subtentorial | Diffuse/Metabolic |
|---|---|---|---|
| Pupils | Normal or dilated with herniation | Midsized (midbrain), pinpoint (pons) | Normal/reactive; pinpoint (opiates); dilated (anticholinergics) |
| Eye movements | May show gaze preference | Abnormal adduction/abduction | Usually preserved unless sedated |
| Motor | Often asymmetric | Asymmetric (uni) or symmetric (bi) | Usually symmetric |
📚 Teaching Commentary
Coma is a syndrome, not a diagnosis. Always think structural vs metabolic. 🔍 Pupils are the fastest localising sign: normal = metabolic, abnormal = structural. 🇬🇧 In UK practice, juniors should remember: “CAND for coma if CT is normal” → Cefotaxime, Aciclovir, Naloxone, Dextrose + Pabrinex. This covers the major reversible killers until more is known. GCS < 8 = intubate. Always immobilise the neck if trauma suspected.
References
Cases - Coma (Reduced GCS)
- Case 1 - Hypoglycaemia: A 58-year-old man with type 2 diabetes on insulin is found unresponsive at home. Capillary glucose is 1.8 mmol/L. GCS 6/15. Pupils equal and reactive. After IV 20% dextrose, consciousness improves rapidly. Teaching point: Always check glucose in any unconscious patient (“D” in ABCDE). Hypoglycaemia is a reversible cause of coma, with rapid recovery if treated promptly. 🍬
- Case 2 - Traumatic brain injury: A 22-year-old motorcyclist is brought in after a high-speed collision. He has unequal pupils (left fixed and dilated), GCS 5/15, and irregular breathing. CT shows an acute left extradural haematoma with midline shift. Teaching point: Low GCS after trauma should prompt urgent neuroimaging. Extradural haematomas may have a classic “lucid interval,” but once coma develops, urgent neurosurgical decompression is required. 🧠
- Case 3 - Sepsis with encephalopathy: A 75-year-old woman with community-acquired pneumonia becomes progressively drowsy. On arrival: temp 39.5°C, BP 80/50, HR 120, GCS 7/15. She localises to pain but does not obey commands. Teaching point: Sepsis-associated encephalopathy is common in older adults; reduced GCS in this setting signals severe illness and high mortality risk. Urgent ABC resuscitation, antibiotics, and source control are priorities. 🌡️
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- Acute Medicine
- Anaesthetics and Critical Care
- Anatomy
- Anatomy and Physiology
- Biochemistry
- Cardiology
- Clinical Genetics
- Clinical Immunology
- Collections
- Critical Care
- Critical care
- Dental
- Dermatology
- Differentials
- Electrocardiogram
- Embryology
- Emergency Medicine
- Endocrinology
- ENT
- Gastroenterology
- Gastroenterology & Hepatology
- General Practice
- Genetics
- Geriatric Medicine
- Guidelines
- Gynaecology
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Infographic
- Investigations
- Lists
- Microbiology
- Nephrology
- Neurology
- Neurology & Stroke
- Neurosurgery
- Obstetrics
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- OSCE
- Paediatrics
- Palliative
- Palliative Medicine
- Pathology
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Renal Medicine
- Respiratory
- Respiratory Medicine
- Resuscitation
- Revision Topics
- Rheumatology
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- Urology
- Vascular Surgery