• AIDS HIV Infection and a Fever โœ…
  • Abacavir ๐Ÿ’Š
  • Abatacept ๐Ÿ’Š
  • Abciximab ๐Ÿ’Š
  • Abdominal Aortic Aneurysm (AAA) โœ…
  • Abdominal Distension
  • Abdominal Masses: Clinical Approach and Considerations
  • Abnormal Involuntary Movements
  • Abnormal eating exercising behaviour (Children)
  • Abnormal urinalysis
  • Acamprosate ๐Ÿ’Š
  • Acarbose ๐Ÿ’Š
  • Acetazolamide ๐Ÿ’Š
  • Aciclovir ๐Ÿ’Š
  • Acoustic Neuroma โœ…
  • Activated Charcoal
  • Actrapid (Insulin) ๐Ÿ’Š
  • Acute (Ascending) Cholangitis โœ…
  • Acute Abdomen - Perforation of a Viscus
  • Acute Abdominal Pain - Children โœ…
  • Acute Airway Obstruction
  • Acute Anaphylaxis โœ…
  • Acute Appendicitis โœ…
  • Acute Bacterial Meningitis (Adults) โœ…
  • Acute Bronchitis โœ…
  • Acute Change in Vision or Vision Loss (OSCE focused)
  • Acute Cholecystitis โœ…
  • Acute Compartment Syndrome
  • Acute Coronary Syndrome (ACS): Chest Pain โค๏ธ
  • Acute Coronary Syndrome: Overview
  • Acute Coronary Syndrome: Unstable Angina
  • Acute Delirium
  • Acute Encephalitis
  • Acute Epiglottitis
  • Acute Glaucoma
  • Acute Hepatitis and Acute Liver disease
  • Acute Hypotension โœ…
  • Acute Kidney Injury โœ…
  • Acute Limb Ischaemia
  • Acute Myocarditis โœ…
  • Acute Pancreatitis โœ…
  • Acute Pericarditis โœ…
  • Acute Pyelonephritis and Urosepsis (UTI) โœ…
  • Acute Renal / Ureteric Colic and Urinary Tract Stones โœ…
  • Acute Respiratory Distress Syndrome (ARDS) โœ…
  • Acute Severe Colitis
  • Acute Stroke Care Guidance UK Ireland 2023
  • Acute and Chronic Diarrhoea โœ…
  • Acutely Ill Critical care patient with High NEWS
  • Adalimumab ๐Ÿ’Š
  • Adefovir ๐Ÿ’Š
  • Adenosine ๐Ÿ’Š
  • Adrenal crises (Paediatric) โœ…
  • Adrenaline (Epinephrine) ๐Ÿ’Š
  • Adult Polycystic kidney disease โœ…
  • Adverse Drug Effects
  • Age-Related Macular Degeneration (ARMD)
  • Alcohol Withdrawal (Delirium Tremens)
  • Alcoholic Hepatitis
  • Alendronate (Alendronic acid) ๐Ÿ’Š
  • Alfacalcidol ๐Ÿ’Š
  • Allergic disorders
  • Allergies
  • Allopurinol ๐Ÿ’Š
  • Alogliptin (Vipidia) ๐Ÿ’Š
  • Alteplase ๐Ÿ’Š
  • Aluminium and Magnesium Antacids
  • Alzheimer disease (Dementia) โœ…
  • Amantadine ๐Ÿ’Š
  • Amenorrhoea
  • Amiloride
  • Aminoglycosides ๐Ÿ’Š
  • Aminophylline ๐Ÿ’Š
  • Aminosalicylates ๐Ÿ’Š
  • Amiodarone ๐Ÿ’Š
  • Amitriptyline ๐Ÿ’Š
  • Amlodipine ๐Ÿ’Š
  • Amoxicillin ๐Ÿ’Š
  • Amphotericin B ๐Ÿ’Š
  • Ampicillin ๐Ÿ’Š
  • Anaemia (Child Health)
  • Anaemia: Assessment โœ…
  • Anagrelide ๐Ÿ’Š
  • Anakinra ๐Ÿ’Š
  • Anal Fissure
  • Andexanet alfa
  • Aneurysms, ischaemic limb and occlusions
  • Angiotensin Converting Enzyme Inhibitors
  • Angiotensin Converting enzyme (ACE) ๐Ÿ’Š
  • Anion Gap and Metabolic Acidosis
  • Ankylosing spondylitis
  • Anogenital Warts (HPV) โœ…
  • Anosmia
  • Antacid medication
  • Anti-D immunoglobulin
  • Anti-OKT3 antibodies
  • Antiarrhythmic agents
  • Antibiotic Guidelines โœ…
  • Antibiotics Mechanisms
  • Anticholinergic Burden
  • Anticoagulation and Antithrombotic
  • Antimicrobial Choices
  • Antimicrobial agents
  • Antimuscarinic drugs ๐Ÿ’Š
  • Anuria and Oliguria
  • Anxiety Phobias and OCD
  • Anxiety disorder: generalised (GAD)
  • Aortic Dissection โœ…
  • Aortic Regurgitation โœ…
  • Aortic Stenosis โœ…
  • Apixaban ๐Ÿ’Š
  • Apomorphine ๐Ÿ’Š
  • Arrhythmias
  • Artemisinins ๐Ÿ’Š
  • Artesunate
  • Arthritis Diagnosis Compared
  • Asbestos Related Lung disease
  • Ascites โœ…
  • Aspirin ๐Ÿ’Š
  • Assessing and Painful Red eye
  • Asthma COPD overlap syndrome
  • Asthma โœ…
  • Atazanavir ๐Ÿ’Š
  • Atenolol ๐Ÿ’Š
  • Atorvastatin ๐Ÿ’Š
  • Atracurium
  • Atrial Fibrillation (AF) ๐Ÿ’“ โœ…
  • Atrial flutter ๐Ÿ’“ โœ…
  • Atropine Sulfate ๐Ÿ’Š
  • Attention deficit hyperactivity disorder
  • Auditory hallucinations
  • Azathioprine ๐Ÿ’Š
  • Azithromycin ๐Ÿ’Š
  • Back pain โœ…
  • Baclofen ๐Ÿ’Š
  • Bacterial Vaginosis
  • Balsalazide (Aminosalicylate) ๐Ÿ’Š
  • Basal Cell Carcinoma (BCC) โœ…
  • Beclometasone (Beclomethasone) ๐Ÿ’Š
  • Behaviour/personality change โœ…
  • Behavioural and Psychological (BPSD) Symptoms of Dementia
  • Behavioural difficulties in Adults โœ…
  • Behavioural difficulties in childhood
  • Bell's Palsy (Facial nerve palsy)
  • Bendroflumethiazide (Bendrofluazide) ๐Ÿ’Š
  • Benign Breast Disease
  • Benign Eyelid Conditions
  • Benign Paroxysmal Positional Vertigo (BPPV)
  • Benign Prostatic Hyperplasia โœ…
  • Benzodiazepines
  • Benzylpenicillin Sodium (Penicillin G) ๐Ÿ’Š
  • Beriplex ๐Ÿ’Š
  • Beta Agonists ๐Ÿ’Š
  • Beta Antagonists/Blockers
  • Beta-lactamases ๐Ÿ’Š
  • Betahistine (Serc) ๐Ÿ’Š
  • Bezafibrate ๐Ÿ’Š
  • Bezafibrate ๐Ÿ’Š
  • Biliary atresia
  • Biological Agents
  • Bisacodyl ๐Ÿ’Š
  • Bisoprolol ๐Ÿ’Š
  • Bisphosphonates ๐Ÿ’Š
  • Bites and stings
  • Blackouts and faints (TLOC)
  • Bleeding Antepartum
  • Bleeding Postpartum
  • Bleomycin
  • Blindness - global causes
  • Blood Pressure
  • Blood Transfusion Reactions
  • Bone Pain
  • Bordetella pertussis (Whooping cough)
  • Brain Abscess
  • Brain Metastases
  • Breast Cancer โœ…
  • Breast Cysts
  • Breast Lump Evaluation
  • Breast abscess and Mastitis and Fat Necrosis
  • Breast tenderness/pain
  • Breathlessness
  • Bretylium ๐Ÿ’Š
  • Bromocriptine ๐Ÿ’Š
  • Bronchiectasis
  • Bronchiolitis
  • Bruising
  • Budesonide ๐Ÿ’Š
  • Bumetanide
  • Buprenorphine ๐Ÿ’Š
  • Bupropion ๐Ÿ’Š
  • Burns Management Guide
  • Busulphan (Busulfan)
  • CNS fungal Infections
  • CNS infections
  • Cabergoline
  • Calcitonin
  • Calcitriol (1,25 Dihydroxycholecalciferol) ๐Ÿ’Š
  • Calcium Channel Blockers
  • Calcium Chloride or Gluconate
  • Calcium Resonium
  • Candesartan ๐Ÿ’Š
  • Candidiasis
  • Capecitabine ๐Ÿ’Š
  • Caplacizumab ๐Ÿ’Š
  • Capreomycin
  • Captopri ๐Ÿ’Š
  • Carbamazepine ๐Ÿ’Š
  • Carbimazole ๐Ÿ’Š
  • Cardiac Troponins
  • Cardiogenic shock
  • Cardiological Emergencies: Revision โœ…
  • Cardiorespiratory Arrest
  • Caring for Patients with Dementia
  • Carmustine ๐Ÿ’Š
  • Carvedilol ๐Ÿ’Š
  • Cataract
  • Cauda Equina Syndrome (CES)
  • Causes of Limp in Children
  • Causes of Neck Pain/Stiffness
  • Causes of Stroke
  • Causes of a Limp in Adults
  • Causes of delayed Onset of Puberty in Children โœ…
  • Cefaclor ๐Ÿ’Š
  • Cefalexin ๐Ÿ’Š
  • Cefotaxime ๐Ÿ’Š
  • Ceftazidime ๐Ÿ’Š
  • Ceftriaxone ๐Ÿ’Š
  • Cefuroxime ๐Ÿ’Š
  • Celecoxib ๐Ÿ’Š
  • Central Retinal Arterial Occlusion (CRAO)
  • Cerebral Palsy & HIE
  • Cervical Cancer screening
  • Cervical Smear Results โœ…
  • Cervical cancer
  • Cervical screening (HPV)
  • Cetirizine ๐Ÿ’Š
  • Change in Bowel habit
  • Change in stool colour
  • Chemotherapeutic Agents
  • Chest Pain
  • Child abuse
  • Childhood Vaccination in the UK
  • Chlamydia Infections
  • Chlorambucil
  • Chloramphenicol ๐Ÿ’Š
  • Chlordiazepoxide ๐Ÿ’Š
  • Chloroquine ๐Ÿ’Š
  • Chlorphenamine(Chlorpheniramine) ๐Ÿ’Š
  • Chlorpromazine ๐Ÿ’Š
  • Chronic Fatigue Syndrome ๐Ÿง 
  • Chronic Glaucoma
  • Chronic Kidney Disease (CKD) โœ…
  • Chronic Obstructive Pulmonary Disease (COPD) โœ…
  • Chronic Rash (Adult/Child)
  • Chronic abdominal pain
  • Chronic joint pain/stiffness ๐Ÿฆด
  • Ciclosporin ๐Ÿ’Š
  • Cimetidine ๐Ÿ’Š
  • Cinacalcet
  • Ciprofloxacin ๐Ÿ’Š
  • Cirrhosis
  • Cisplatin
  • Citalopram ๐Ÿ’Š
  • Cladribine
  • Clarithromycin ๐Ÿ’Š
  • Clindamycin ๐Ÿ’Š
  • Clinical Appearance Collections
  • Clonidine ๐Ÿ’Š
  • Clopidogrel ๐Ÿ’Š
  • Clotrimazole cream ๐Ÿ’Š
  • Clozapine ๐Ÿ’Š
  • Co Careldopa (Sinemet)
  • Co-Beneldopa (Madopar)
  • Co-codamol ๐Ÿ’Š
  • Co-trimoxazole (Trimethoprim + Sulfamethoxazole) ๐Ÿ’Š
  • CoAmoxiclav (Augmentin) ๐Ÿ’Š
  • Codeine ๐Ÿ’Š
  • Coeliac disease โœ…
  • Colchicine ๐Ÿ’Š
  • Colorectal tumours โœ…
  • Combined Oral contraceptive pill (COCP) ๐Ÿ’Š
  • Community Acquired Pneumonia ๐Ÿซ โœ…
  • Comprehensive Geriatric Assessment (CGA)
  • Confusion (OSCE focused)
  • Congenital abnormalities
  • Conjunctivitis
  • Constipation (Adults) โœ…
  • Contact Dermatitis
  • Contraception request/advice โœ…
  • Cord Prolapse
  • Coronavirus SARS-CoV-2 (COVID-19) โœ…
  • Corticosteroid-related psychosis ๐Ÿ’Š
  • Corticosteroids: Uses and Cautions
  • Cough (Adult)
  • Croup
  • Cryptogenic Organising Pneumonia (COP-BOOP)
  • Crystal arthropathy
  • Cushing syndrome
  • Cutaneous Warts
  • Cutaneous fungal infections
  • Cyclizine
  • Cyclo-oxygenase (COX) enzymes
  • Cyclophosphamide ๐Ÿ’Š
  • Cycloserine
  • Cys leukotriene receptor antagonists ๐Ÿ’Š
  • Cystic Fibrosis โœ…
  • Dabigatran ๐Ÿ’Š
  • Dalteparin ๐Ÿ’Š
  • Dantrolene ๐Ÿ’Š
  • Dapagliflozin ๐Ÿ’Š
  • Darunavir ๐Ÿ’Š
  • Death and dying
  • Decreased appetite
  • Deep Vein Thrombosis (DVT) โœ…
  • Dehydration (Child)
  • Dehydration Adult
  • Demeclocycline ๐Ÿ’Š
  • Dementias
  • Dengue Fever
  • Denosumab (Prolia) ๐Ÿ’Š
  • Dermatology Emergencies โœ…
  • Desferrioxamine ๐Ÿ’Š
  • Desmopressin (DDAVP) ๐Ÿ’Š
  • Desogestrel (Progestogen Only Pill) ๐Ÿ’Š
  • Developmental Delay & Abnormal Development in Children
  • Dexamethasone ๐Ÿ’Š
  • Diabetes Insipidus (AVP Deficiency)
  • Diabetes Mellitus Type 1 โœ…
  • Diabetes Mellitus Type 2 โœ…
  • Diabetic Eye Disease
  • Diabetic Ketoacidosis (DKA) Adults โœ…
  • Diabetic Ketoacidosis (DKA) Children
  • Diabetic nephropathy
  • Diabetic neuropathy
  • Diamorphine ๐Ÿ’Š
  • Diazepam ๐Ÿ’Š
  • Didanosine (ddI) ๐Ÿ’Š
  • Diethylstilbestrol
  • Difficulty with breastfeeding
  • Digoxin ๐Ÿ’Š
  • Dihydrocodeine ๐Ÿ’Š
  • Diltiazem ๐Ÿ’Š
  • Diplopia (Double Vision)
  • Dipyridamole ๐Ÿ’Š
  • Disease prevention/screening
  • Disopyramide ๐Ÿ’Š
  • Disseminated Intravascular Coagulation (DIC)
  • Disulfiram (Antabuse) ๐Ÿ’Š
  • Diuretics
  • Diverticular disease and Acute Diverticulitis โœ…
  • Dizziness
  • Dobutamine ๐Ÿ’Š
  • Dog Bites โœ…
  • Domperidone ๐Ÿ’Š
  • Donepezil (Aricept) ๐Ÿ’Š
  • Dopamine Hydrochloride ๐Ÿ’Š
  • Dopamine agonists ๐Ÿ’Š
  • Dosing Gentamicin
  • Downs syndrome
  • Doxapram ๐Ÿ’Š
  • Doxazosin (Cardura) ๐Ÿ’Š
  • Doxepin ๐Ÿ’Š
  • Doxorubicin (Adriamycin)
  • Doxycycline ๐Ÿ’Š
  • Driving Advice
  • Drug Metabolism
  • Drug Overdose Adults
  • Drug overdose children โœ…
  • Drugs to Avoid in Acute Renal failure
  • Drugs to avoid in Liver failure
  • Dry and Wet and Gas Gangrene
  • Duchenne Muscular Dystrophy
  • Dulaglutide GLP-1 agonist ๐Ÿ’Š
  • Duloxetine ๐Ÿ’Š
  • Dysmorphic child
  • ECG - Acute Coronary Syndrome โค๏ธ
  • ECG - Hyperkalaemia โค๏ธ
  • ECG Reading & Interpretation MLA and Exams ๐Ÿซ€
  • ENT Emergencies: Revision โœ…
  • ENT infections
  • Ear Pain (Otalgia)
  • Ear and Nasal Discharge
  • Eating Disorders
  • Ectopic Pregnancy
  • Eculizumab ๐Ÿ’Š
  • Eczema/Dermatitis
  • Edoxaban (Lixiana)
  • Efavirenz (Sustiva) EFV ๐Ÿ’Š
  • Elation/elated mood
  • Elder Abuse and Safeguarding
  • Electrolyte Abnormalities
  • Emtricitabine (Emtriva) FTC ๐Ÿ’Š
  • Enalapril ๐Ÿ’Š
  • Endocrine Emergencies: Revision โœ…
  • Endometrial (Uterine) Cancer
  • Endometriosis
  • Enfuvirtide ๐Ÿ’Š
  • Enoxaparin Sodium (Clexane-Lovenox) ๐Ÿ’Š
  • Enoximone ๐Ÿ’Š
  • Entacapone
  • Enzyme inducers and inhibitors
  • Epididymitis and Orchitis (Children) โœ…
  • Epididymitis and Orchitis in Adults
  • Epilepsy โœ…
  • Epistaxis
  • Eplerenone ๐Ÿ’Š
  • Erectile dysfunction
  • Ergocalciferol (Calciferol) ๐Ÿ’Š
  • Erlotinib (Tarceva) ๐Ÿ’Š
  • Erythema Nodosum
  • Erythromycin ๐Ÿ’Š
  • Escitalopram ๐Ÿ’Š
  • Esomeprazole ๐Ÿ’Š
  • Essential Hypertension โœ…
  • Essential Tremor
  • Etanercept ๐Ÿ’Š
  • Ethambutol ๐Ÿ’Š
  • Ethanol ๐Ÿ’Š
  • Etomidate
  • Etravirine (intelence) ETR ๐Ÿ’Š
  • Exenatide (Byetta) GLP1 agonist ๐Ÿ’Š
  • Extradural haemorrhage
  • Extrapyramidal symptoms
  • Eye Trauma
  • Eye pain/discomfort
  • Ezetimibe ๐Ÿ’Š
  • Facial and Periorbital Swelling
  • Facial pain
  • Faecal Incontinence
  • Falls
  • Family history of possible genetic disorder
  • Famotidine ๐Ÿ’Š
  • Fasciculation
  • Febrile convulsion
  • Felodipine (Dihydropyridine)
  • Fentanyl - Fentanil
  • Ferrous Fumarate - Gluconate - Sulphate ๐Ÿ’Š
  • Fever - all ages
  • Fibrotic Lung Disease
  • Fidaxomicin ๐Ÿ’Š
  • Finasteride (5 alpha-reductase inhibitor) ๐Ÿ’Š
  • First Seizure
  • Fit Notes in General Practice (UK)
  • Fixed Abnormal Beliefs (Delusions)
  • Flashes and Floaters in the Visual Field
  • Flecainide Acetate ๐Ÿ’Š
  • Flucloxacillin ๐Ÿ’Š
  • Fluconazole ๐Ÿ’Š
  • Flucytosine ๐Ÿ’Š
  • Fludrocortisone ๐Ÿ’Š
  • Flumazenil (Annexate - Romazicon) ๐Ÿ’Š
  • Fluoxetine ๐Ÿ’Š
  • Folate (Folic) acid (B9) ๐Ÿ’Š
  • Folinic acid (Leucovorin) ๐Ÿ’Š
  • Folliculitis
  • Fomepizole ๐Ÿ’Š
  • Fondaparinux ๐Ÿ’Š
  • Food Intolerance in Children
  • Foreign Body in Eye
  • Foscarnet Sodium ๐Ÿ’Š
  • Fosfomycin
  • Fosphenytoin ๐Ÿ’Š
  • Fractured Neck of Femur/Femoral Neck
  • Frailty an Overview
  • Full or Complete Blood Count (FBC CBC)
  • Furosemide (Frusemide)
  • Fusidic acid ๐Ÿ’Š
  • Gabapentin ๐Ÿ’Š
  • Galantamine
  • Gallstones and biliary colic
  • Ganciclovir - Valganciclovir ๐Ÿ’Š
  • Gas Gangrene (Clostridial Myonecrosis)
  • Gastric Cancer โœ…
  • Gastroenteritis in Adults โœ…
  • Gastroenteritis in Children
  • Gastrointestinal Emergencies: Revision โœ…
  • General Basic Fracture management โœ…
  • Genital Ulcers
  • Gentamicin ๐Ÿ’Š
  • Gestational Diabetes Mellitus โœ…
  • Glatiramer acetate (Copaxone) ๐Ÿ’Š
  • Glibenclamide ๐Ÿ’Š
  • Gliclazide
  • Glimepiride
  • Glipizide
  • Glucagon ๐Ÿ’Š
  • Glyceryl Trinitrate (GTN) ๐Ÿ’Š
  • Glycopyrronium Bromide
  • Golimumab (Simponi) ๐Ÿ’Š
  • Gonorrhoea
  • Goserelin (Zoladex) ๐Ÿ’Š
  • Gradual change in or loss of vision
  • Griseofulvin ๐Ÿ’Š
  • Gynaecomastia โœ…
  • Haematology Emergencies: Revision โœ…
  • Haemoglobinopathies
  • Haemophilia A โœ…
  • Haemoptysis
  • Haemorrhagic stroke
  • Haemorrhoids (Piles) โœ…
  • Haloperidol ๐Ÿ’Š
  • Hartmanns solution (Ringers lactate) ๐Ÿ’Š
  • Head Injury and Traumatic Brain Head Injury (TBI)
  • Head Lice
  • Headaches
  • Heart Failure with preserved and reduced EF โœ…
  • Heart Murmurs
  • Heparin - General ๐Ÿ’Š
  • Heparin - Low Molecular Weight Heparin ๐Ÿ’Š
  • Heparin - Unfractionated Heparin ๐Ÿ’Š
  • Hepatology Emergencies: Revision
  • Hereditary Haemochromatosis
  • Hernias (Children)
  • Herpes Simplex Virus
  • Herpes Varicella-Zoster (Shingles) Infection
  • Hiatus hernia
  • Hoarseness and voice change
  • Hodgkin vs Non-Hodgkin Lymphoma:
  • Hospital-acquired infections
  • Human albumin solution (HAS)
  • Human papilloma virus infection
  • Hydralazine ๐Ÿ’Š
  • Hydrocortisone ๐Ÿ’Š
  • Hydroxocobalamin - Cyanocobalamin (B12) ๐Ÿ’Š
  • Hydroxocobalamin ๐Ÿ’Š
  • Hydroxychloroquine ๐Ÿ’Š
  • Hyoscine (Buscopan) ๐Ÿ’Š
  • Hyperacute Stroke Care Pathway
  • Hypercalcaemia of Malignancy
  • Hypercalcaemia โœ…
  • Hyperemesis Gravidarum
  • Hyperglycaemic Hyperosmolar State (HHS) โœ…
  • Hyperkalaemia โœ…
  • Hyperlipidaemia
  • Hyperparathyroidism
  • Hyperphosphataemia (High phosphate)
  • Hypertension in Children โœ…
  • Hypertension in Pregnancy โœ…
  • Hyperthermia and Hypothermia
  • Hypocalcaemia โœ…
  • Hypoglycaemia
  • Hypokalaemia
  • Hypomagnesaemia โœ…
  • Hyponatraemia โœ…
  • Hypophosphataemia (Low phosphate)
  • Hypothyroidism โœ…
  • Hypoxic-Ischaemic Encephalopathy
  • IV Immunoglobulin (IVIG) ๐Ÿ’Š
  • Ibandronic acid (Bisphosphonate) ๐Ÿ’Š
  • Ibuprofen ๐Ÿ’Š
  • Icatibant ๐Ÿ’Š
  • Idarucizumab (Praxbind) ๐Ÿ’Š
  • Idiopathic Arthritis in Adults
  • Imaging for the MLA#1
  • Imaging for the MLA#2
  • Imatinib mesylate
  • Imipenem (Primaxin) with Cilastin ๐Ÿ’Š
  • Immobility
  • Impetigo
  • Incidental Findings (Incidentalomas)
  • Indapamide ๐Ÿ’Š
  • Indinavir (IND)
  • Infant feeding issues
  • Infectious Colitis
  • Infectious Diarrhoea (OSCE focused)
  • Infectious Mononucleosis (EBV Most Often)
  • Infective Endocarditis
  • Infective Keratitis
  • Infertility & Subfertility
  • Inflammatory Bowel Disease
  • Infliximab ๐Ÿ’Š
  • Insulin Degludec (Tresiba)
  • Insulin Detemir (Levemir)
  • Insulin Glargine (Lantus, Abasaglar, Semglee, Toujeo)
  • Interferon Beta ๐Ÿ’Š
  • Intestinal Ischaemia
  • Intestinal obstruction and Ileus
  • Intrauterine death โœ…
  • Intravenous Iron Replacement
  • Intussusception in Adults
  • Ipratropium Bromide (Atrovent) ๐Ÿ’Š
  • Irbesartan ๐Ÿ’Š
  • Iritis (Anterior Uveitis)
  • Iron Salts ๐Ÿ’Š
  • Irritable bowel syndrome โœ…
  • Isoniazid ๐Ÿ’Š
  • Isoprenaline ๐Ÿ’Š
  • Isosorbide Dinitrate ๐Ÿ’Š
  • Isosorbide mononitrate ๐Ÿ’Š
  • Isotretinoin (Accutane) ๐Ÿ’Š
  • Ispaghula Husk (Fybogel) ๐Ÿ’Š
  • Ivabradine ๐Ÿ’Š
  • Jaundice
  • Kawasaki disease
  • Ketamine ๐Ÿ’Š
  • Ketoconazole ๐Ÿ’Š
  • L-Thyroxine (T4) ๐Ÿ’Š
  • Labetalol (Trandate) ๐Ÿ’Š
  • Labour and Complications
  • Lacerations
  • Lactulose ๐Ÿ’Š
  • Lacunar Stroke Syndromes
  • Lamivudine (3TC) ๐Ÿ’Š
  • Lamotrigine ๐Ÿ’Š
  • Lansoprazole ๐Ÿ’Š
  • Lanthanum
  • Large for Gestational Age (LGA)
  • Laxatives ๐Ÿ’Š
  • Learning (Intellectual) disability
  • Leflunomide (Arava) ๐Ÿ’Š
  • Lenalidomide (Revlimid)
  • Leukaemia
  • Levetiracetam (Keppra) ๐Ÿ’Š
  • Levodopa ๐Ÿ’Š
  • Levomepromazine
  • Levosimendan ๐Ÿ’Š
  • Lidocaine(Lignocaine) ๐Ÿ’Š
  • Limb Weakness
  • Linagliptin (Trajenta) ๐Ÿ’Š
  • Linezolid
  • Liothyronine Sodium L-Triiodothyronine (T3) ๐Ÿ’Š
  • Lipid emulsion therapy - Intralipid ๐Ÿ’Š
  • Liraglutide (Victoza) ๐Ÿ’Š
  • Lisinopril ๐Ÿ’Š
  • Lithium ๐Ÿ’Š
  • Lofepramine ๐Ÿ’Š
  • Loin Pain
  • Loop diuretics ๐Ÿ’Š
  • Loperamide ๐Ÿ’Š
  • Lopinavir ๐Ÿ’Š
  • Loratadine ๐Ÿ’Š
  • Lorazepam ๐Ÿ’Š
  • Losartan ๐Ÿ’Š
  • Loss of Libido
  • Loss of red reflex
  • Low mood/affective/depression problems
  • Lower Gastrointestinal Bleeding โœ…
  • Lower Limb Fractures
  • Lower Limb Soft Tissue Injuries
  • Lower respiratory tract infection (Child)
  • Lugol iodine ๐Ÿ’Š
  • Lump in Groin
  • Lung Cancer
  • Lyme disease
  • Lymphadenopathy
  • Magnesium Physiology
  • Magnesium Sulphate - Sulfate
  • Malaria
  • Malignant Breast Disease
  • Malignant Hyperpyrexia (Malignant Hyperthermia)
  • Malignant Hypertension
  • Malignant Melanoma โœ…
  • Malnutrition Adults and the Elderly
  • Malnutrition in Children ๐Ÿฝ๏ธ
  • Mannitol
  • Maraviroc (Celsentri) ๐Ÿ’Š
  • Massive Haemorrhage and Massive Transfusion Protocol (MTP)
  • Measles (notifiable)
  • Mebeverine ๐Ÿ’Š
  • Mefenamic acid ๐Ÿ’Š
  • Mefloquine (Larium)
  • Melaena
  • Melatonin
  • Memantine Hydrochloride ๐Ÿ’Š
  • Memory Loss
  • Menieres disease
  • Menopause and Menopausal Problems ๐ŸŒธ โœ…
  • Menstrual problems
  • Mental capacity concerns
  • Mental health problems in pregnancy or postpartum ๐Ÿคฐ
  • Mercaptopurine ๐Ÿ’Š
  • Meropenem ๐Ÿ’Š
  • Mesalazine (Aminosalicylate) ๐Ÿ’Š
  • Mesenteric adenitis
  • Metabolic acidosis
  • Metabolic alkalosis
  • Metastatic disease
  • Metformin ๐Ÿ’Š
  • Methodone ๐Ÿ’Š
  • Methotrexate ๐Ÿ’Š
  • Methylcellulose ๐Ÿ’Š
  • Methylprednisolone
  • Metoclopramide ๐Ÿ’Š
  • Metolazone ๐Ÿ’Š
  • Metoprolol ๐Ÿ’Š
  • Metronidazole (Flagyl) ๐Ÿ’Š
  • Metyrapone (Metopirone) ๐Ÿ’Š
  • Miconazole ๐Ÿ’Š
  • Midazolam
  • Midodrine ๐Ÿ’Š
  • Migraine โœ…
  • Milrinone
  • Minocycline ๐Ÿ’Š
  • Minoxidil ๐Ÿ’Š
  • Mirabegron ๐Ÿ’Š
  • Mirtazapine ๐Ÿ’Š
  • Miscarriage
  • Misoprostol ๐Ÿ’Š
  • Misplaced Nasogastric tube insertion
  • Mitral Regurgitation (Incompetence)
  • Mitral Stenosis โœ…
  • Montelukast ๐Ÿ’Š
  • Morphine Sulphate ๐Ÿ’Š
  • Motor Neuron Disease (MND-ALS)
  • Multiple Myeloma
  • Multiple Organ Dysfunction Syndrome
  • Multiple Sclerosis (MS)
  • Mumps (Notifiable)
  • Muscle Pain Myalgia
  • Muscular Dystrophies
  • Musculoskeletal deformities
  • Musculoskeletal deformities
  • Myasthenia Gravis
  • Mycophenolate mofetil ๐Ÿ’Š
  • Myeloproliferative disorders โœ…
  • N-Acetylcysteine (Parvolex) ๐Ÿ’Š
  • Naloxone (Narcan) Opiate antagonist ๐Ÿ’Š
  • Naproxen
  • Nasal Discharge
  • Natalizumab (Tysabri) ๐Ÿ’Š
  • National Institutes of Health Stroke Scale (NIHSS)
  • Necrotising Enterocolitis
  • Necrotising fasciitis
  • Nefopam ๐Ÿ’Š
  • Neomycin ๐Ÿ’Š
  • Neonatal death or cot death
  • Neostigmine ๐Ÿ’Š
  • Nephrotic Syndrome in Children โœ…
  • Nephrotic syndrome in Adults
  • Nephrotoxic drugs
  • Neuromuscular weakness
  • Neutropenic Sepsis
  • Nevirapine (Viramune) NEV-NVP ๐Ÿ’Š
  • Nicardipine (Cardene)
  • Nicorandil ๐Ÿ’Š
  • Nifedipine ๐Ÿ’Š
  • Night sweats
  • Nimodipine (Nimotop) ๐Ÿ’Š
  • Nipple Discharge
  • Nitrates
  • Nitrofurantoin ๐Ÿ’Š
  • Nizatidine ๐Ÿ’Š
  • Non steroidal anti inflammatory drugs (NSAIDs) ๐Ÿ’Š
  • Non-accidental injury
  • Noradrenaline (Norepinephrine) ๐Ÿ’Š
  • Normal pregnancy and Antenatal care
  • Nortriptyline ๐Ÿ’Š
  • Nosocomial infections
  • Nutrition in Infants Breastfeeding
  • Nystatin ๐Ÿ’Š
  • OSCE Dysphagia Swallowing
  • Obesity
  • Obesity and Pregnancy
  • Obstetrics Emergencies: Revision โœ…
  • Obstructive Sleep Apnoea
  • Octreotide ๐Ÿ’Š
  • Oesophageal Carcinoma
  • Olanzapine ๐Ÿ’Š
  • Olmersartan ๐Ÿ’Š
  • Olsalazine (Aminosalicylate) ๐Ÿ’Š
  • Omalizumab
  • Omeprazole ๐Ÿ’Š
  • Ondansetron ๐Ÿ’Š
  • Ophthalmic Emergencies: Revision โœ…
  • Opiates ๐Ÿ’Š
  • Opicapone ๐Ÿ’Š
  • Optic Neuritis
  • Orbital Cellulitis vs Preorbital Cellulitis
  • Organomegaly
  • Orphenadrine
  • Orthostatic Hypotension
  • Oseltamivir - Tamiflu ๐Ÿ’Š
  • Osteoarthritis
  • Osteomalacia
  • Osteomyelitis โœ…
  • Osteoporosis โœ…
  • Otitis Externa (Malignant)
  • Otitis Media
  • Ovarian Cancer
  • Oxybutynin (Ditropan) ๐Ÿ’Š
  • Oxycodone (Oxycontin-Oxynorm) ๐Ÿ’Š
  • Oxytetracycline ๐Ÿ’Š
  • Pabrinex ๐Ÿ’Š
  • Pain Management: Acute & Chronic
  • Pain on inspiration
  • Painful Sexual Intercourse (Dyspareunia)
  • Painful swollen leg
  • Palliation - Nausea Dyspnoea Secretions Pain
  • Pallor
  • Palpitations
  • Pamidronate (Bisphosphonate) ๐Ÿ’Š
  • Pancreatic Cancer
  • Pancytopenia
  • Pantoprazole ๐Ÿ’Š
  • Paracetamol (Acetaminophen) ๐Ÿ’Š
  • Parkinson disease
  • Paroxetine ๐Ÿ’Š
  • Pathological bone fracture
  • Patient on Anticoagulant and Antiplatelet Therapy
  • Patiromer ๐Ÿ’Š
  • Pegvisomant ๐Ÿ’Š
  • Pelvic Inflammatory Disease โœ…
  • Pelvic Mass
  • Pelvic Pain
  • Penicillamine ๐Ÿ’Š
  • Penicillin Allergy
  • Penicillins ๐Ÿ’Š
  • Peptic ulcer disease (PUD) and gastritis in Children
  • Peptic ulcer disease and Gastritis in Adults
  • Pergolide
  • Perianal abscesses and fistulae โœ…
  • Perianal symptoms
  • Pericardial Disease
  • Pericardial Effusion and Tamponade โœ…
  • Perindopril ๐Ÿ’Š
  • Peripheral oedema and ankle swelling
  • Peritonitis
  • Petechial Rash in Adult or Child
  • Pethidine
  • Pharmacokinetic
  • Pharmacokinetics
  • Phenobarbital sodium
  • Phenoxymethylpenicillin (Penicillin V) ๐Ÿ’Š
  • Phentolamine ๐Ÿ’Š
  • Phenytoin (Dilantin) ๐Ÿ’Š
  • Picolax - Citrafleet ๐Ÿ’Š
  • Pioglitazone (Thiazolidinediones) ๐Ÿ’Š
  • Pituitary Tumours
  • Pivmecillinam (a penicillin antibiotic) ๐Ÿ’Š
  • Pleural effusion
  • Poisoning
  • Polycythaemia
  • Polydipsia (thirst)
  • Polymyalgia Rheumatica
  • Polypharmacy and STOPP/START criteria
  • Post Menopausal Bleeding
  • Pralidoxime ๐Ÿ’Š
  • Pramipexole (Mirapexin) ๐Ÿ’Š
  • Prasugrel ๐Ÿ’Š
  • Pravastatin ๐Ÿ’Š
  • Praziquantel
  • Prazosin ๐Ÿ’Š
  • Pre-eclampsia, Gestational Hypertension
  • Prednisolone ๐Ÿ’Š
  • Prednisone ๐Ÿ’Š
  • Pregabalin ๐Ÿ’Š
  • Pregnancy risk assessment
  • Prematurity
  • Premed Pharmacology
  • Prescribing in Pregnancy
  • Pressure sores or ulcers
  • Primaquine
  • Probenecid ๐Ÿ’Š
  • Prochlorperazine (Stemetil) ๐Ÿ’Š
  • Procyclidine
  • Propafenone ๐Ÿ’Š
  • Propantheline ๐Ÿ’Š
  • Propofol ๐Ÿ’Š
  • Propranolol ๐Ÿ’Š
  • Propylthiouracil ๐Ÿ’Š
  • Protamine Sulfate ๐Ÿ’Š
  • Prothrombin Complex Concentrates (Octaplex and Beriplex) ๐Ÿ’Š
  • Prucalopride
  • Pruritis
  • Psoriasis
  • Pubertal Development
  • Pulmonary Embolism ๐Ÿซ
  • Pulmonary Hypertension
  • Purpura
  • Pyloric Stenosis Children
  • Pyrazinamide ๐Ÿ’Š
  • Pyridostigmine ๐Ÿ’Š
  • Quetiapine ๐Ÿ’Š
  • Quinine ๐Ÿ’Š
  • Radiculopathies
  • Raised intracranial pressure (ICP)
  • Raloxifene ๐Ÿ’Š
  • Raltegravir ๐Ÿ’Š
  • Ramipril ๐Ÿ’Š
  • Ranitidine ๐Ÿ’Š
  • Ranolazine ๐Ÿ’Š
  • Rapid Sequence Intubation (RSI)
  • Rasagiline ๐Ÿ’Š
  • Rasburicase
  • Rectal Prolapse โœ…
  • Reduced/change in fetal movements
  • Remdesvir (Veklury)
  • Renal Emergencies: Revision โœ…
  • Renal Replacement Therapy (RRT)
  • Renal Tubular Acidosis (RTA)
  • Respiratory Arrest
  • Respiratory Emergencies: Revision โœ…
  • Respiratory Failure
  • Resus: Septic Shock and Sepsis
  • Reteplase ๐Ÿ’Š
  • Retinal detachment
  • Retinoids ๐Ÿ’Š
  • Rheumatology Drugs
  • Rhinosinusitis
  • Ribavirin ๐Ÿ’Š
  • Rifampicin (Rifabutin Rifampin) ๐Ÿ’Š
  • Rifaximin ๐Ÿ’Š
  • Right heart valve disease
  • Rilipivirine (Edurant) RVP ๐Ÿ’Š
  • Riluzole (Rilutek)
  • Risedronate (Bisphosphonate) ๐Ÿ’Š
  • Risperidone ๐Ÿ’Š
  • Ritonavir (Norvir) RTV ๐Ÿ’Š
  • Rituximab (Mabthera) ๐Ÿ’Š
  • Rivaroxaban (Xarelto) ๐Ÿ’Š
  • Rivastigmine (Exelon) ๐Ÿ’Š
  • Rocuronium ๐Ÿ’Š
  • Rotigotine Transdermal Patch (Neupro) ๐Ÿ’Š
  • Rubella (German Measles) Notifiable
  • Sacubitril with Valsartan ๐Ÿ’Š
  • Saquinavir (Invirase) SQV ๐Ÿ’Š
  • Sarcoidosis
  • Saxagliptin (Onglyza) ๐Ÿ’Š
  • Scabies
  • Schizophrenia
  • Scleritis
  • Scrotal/testicular pain/lump/swelling โš ๏ธ
  • Secondary Hypertension
  • Selective serotonin reuptake inhibitors (SSRI) ๐Ÿ’Š
  • Selegiline ๐Ÿ’Š
  • Self-harm / Suicidal thoughts / Suicide โœ…
  • Senna ๐Ÿ’Š
  • Sevelamer ๐Ÿ’Š
  • Shock in Pregnancy
  • Sick Child/Neonate
  • Sickle Cell Disease
  • Sigmoid and Caecal Volvulus Adults
  • Sildenafil (Viagra) ๐Ÿ’Š
  • Simvastatin ๐Ÿ’Š
  • Sitagliptin ๐Ÿ’Š
  • Skin Ulcers
  • Skin and soft tissue and bone infections โœ…
  • Small for Gestational Age (SGA)
  • Sodium Nitroprusside ๐Ÿ’Š
  • Sodium Picosulfate ๐Ÿ’Š
  • Sodium Thiopental - Sodium Thiopentone ๐Ÿ’Š
  • Sodium Valproate (Epilim Depakote) ๐Ÿ’Š
  • Sodium Zirconium Cyclosilicate (Lokelma)
  • Sodium Zirconium Cyclosilicate ๐Ÿ’Š
  • Soft Tissue Injury
  • Solifenacin ๐Ÿ’Š
  • Somatisation
  • Somatisation/medically unexplained physical symptoms
  • Sore throat
  • Sotalol Hydrochloride ๐Ÿ’Š
  • Speech and language problems
  • Spinal Cord Compression
  • Spinal Cord Injury / Malignant Spinal Cord Compression (MSCC)
  • Spinal Fracture
  • Spironolactone ๐Ÿ’Š
  • Splenectomy and Hyposplenism
  • Squamous Cell Carcinoma
  • Squint
  • St John's Wort ๐Ÿ’Š
  • Staphylococcal Infections
  • Statin ๐Ÿ’Š
  • Status Epilepticus (Epilepsy/Seizure)
  • Stavudine (Zerit) d4T ๐Ÿ’Š
  • Streptokinase ๐Ÿ’Š
  • Streptomycin ๐Ÿ’Š
  • Stridor
  • Stroke
  • Stroke Mimics And Chameleons
  • Stroke Risk Factors
  • Strontium ๐Ÿ’Š
  • Subarachnoid Haemorrhage โœ…
  • Subdural haematoma
  • Subfertility in Men
  • Subfertility in Women
  • Substance misuse
  • Substance use disorder
  • Sucralfate ๐Ÿ’Š
  • Sugammadex ๐Ÿ’Š
  • Suicidal thoughts
  • Suicide
  • Sulfasalazine - Sulphasalazine ๐Ÿ’Š
  • Sumatriptan
  • Supraventricular Tachycardia (SVT)
  • Surgical Liaison in Older Patients Quality & Silver Trauma (UK)
  • Surgical site infection
  • Suxamethonium ๐Ÿ’Š
  • Syphilis
  • Systemic Lupus Erythematosus (SLE) โœ…
  • TNF Blockade
  • Tacrolimus ๐Ÿ’Š
  • Tafamidis
  • Tamoxifen
  • Tamsulosin (Flomax) ๐Ÿ’Š
  • Tazocin (Tazobactam - Piperacillin) ๐Ÿ’Š
  • Teicoplanin ๐Ÿ’Š
  • Temazepam ๐Ÿ’Š
  • Temozolomide (Temodal) ๐Ÿ’Š
  • Tenecteplase ๐Ÿ’Š
  • Tension Headache
  • Terbutaline
  • Teriparatide ๐Ÿ’Š
  • Terlipressin
  • Testicular Cancer
  • Testicular Torsion โœ…
  • Tetrabenazine
  • Tetracosactide (Synacthen)
  • Tetracyclines ๐Ÿ’Š
  • Thalidomide ๐Ÿ’Š
  • The Deteriorating Patient
  • The Fetal Head and Vaginal Birth
  • The unconscious (comatose) patient
  • Theophylline ๐Ÿ’Š
  • Thiamine ๐Ÿ’Š
  • Thyroid Eye Disease
  • Thyroid nodules โœ…
  • Thyrotoxicosis and Hyperthyroidism
  • Tiagabine ๐Ÿ’Š
  • Ticagrelor
  • Timolol
  • Tinidazole
  • Tinnitus
  • Tinzaparin (Innohep) ๐Ÿ’Š
  • Tiotropium (Spiriva) ๐Ÿ’Š
  • Tocilizumab ๐Ÿ’Š
  • Tolbutamide
  • Tolcapone ๐Ÿ’Š
  • Tolterodine ๐Ÿ’Š
  • Tolvaptan
  • Tonsilitis
  • Topiramate (Topamax) ๐Ÿ’Š
  • Toxic Shock Syndrome โœ…
  • Toxicological Emergencies
  • Tramadol ๐Ÿ’Š
  • Tranexamic Acid ๐Ÿ’Š
  • Transient Ischaemic Attack (TIA)
  • Trastuzumab (Herceptin) ๐Ÿ’Š
  • Trauma
  • Trauma: Spinal Injury
  • Travel health advice
  • Trazodone ๐Ÿ’Š
  • Trichomoniasis Vaginalis โœ…
  • Trigeminal Neuralgia
  • Trihexyphenidyl (benzhexol)
  • Trimethoprim ๐Ÿ’Š
  • Tuberculosis
  • Unintentional weight loss (Adults)
  • Unsteadiness
  • Unwanted pregnancy and termination
  • Upper Gastrointestinal Bleed โœ…
  • Upper Limb fractures and injuries
  • Upper limb Soft Tissue Injuries
  • Upper respiratory tract infection
  • Urethral Discharge (Urethritis)
  • Urinary Incontinence โœ…
  • Urinary Obstruction
  • Urinary Tract Obstruction
  • Urinary symptoms
  • Urticaria
  • Uterine fibroids
  • Uveitis โœ…
  • Vaginal Prolapse
  • Valaciclovir ๐Ÿ’Š
  • Valsartan ๐Ÿ’Š
  • Vancomycin ๐Ÿ’Š
  • Variable rate intravenous insulin infusion VRIII ๐Ÿ’Š
  • Varicose veins โœ…
  • Vasa Praevia
  • Vascular Dementia
  • Vasopressin (AVP) Antidiuretic hormone
  • Vasovagal syncope (OSCE focused)
  • Vecuronium ๐Ÿ’Š
  • Vedolizumab (Entyvio)
  • Venlafaxine ๐Ÿ’Š
  • Venous Insufficiency and Leg Ulcers
  • Venous Thromboembolism Pregnancy and Puerperium
  • Venous and Arterial and Pressure Ulcers
  • Ventricular Tachycardia VT โœ…
  • Verapamil ๐Ÿ’Š
  • Vigabatrin (Sabril) ๐Ÿ’Š
  • Vinblastine
  • Vincristine
  • Viral Gastroenteritis and other causes
  • Viral exanthema โœ…
  • Viral hepatitides
  • Visual Hallucinations in the elderly
  • Vitamin D Replacement
  • Vitamin K (Phytomenadione)
  • Voltarol (Diclofenac)
  • Volvulus (Children)
  • Vulval itching and lesions
  • Vulval/vaginal lump
  • Warfarin ๐Ÿ’Š
  • Weight Gain Adults
  • Wellbeing Checks in General Practice for GPs
  • Wernicke Korsakoff Syndrome
  • Zidovudine (Retrovir) AZT - ZDV ๐Ÿ’Š
  • Zoledronic acid (Zoledronate) ๐Ÿ’Š
  • Zolpidem ๐Ÿ’Š
  • Zopiclone ๐Ÿ’Š
  • intedanib (Ofevยฎ) ๐Ÿ’Š
  • Download the amazing global Makindo app: โœ… Means NICE/National Guidelines 2026 compliant Android | Apple
    MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer.

    Acute Coronary Syndrome: Overview

    โค๏ธ Myocardial Infarction (MI) is necrosis of cardiac muscle due to prolonged ischaemia, usually from coronary artery thrombosis. Rapid recognition and early reperfusion therapy reduce mortality. ACS also includes unstable angina and NSTEMI.

    ๐Ÿ”ฌ Pathophysiology
    • ๐Ÿ“‰ Atherosclerotic plaque rupture โ†’ platelet aggregation โ†’ thrombus โ†’ coronary occlusion.
    • โšก Oxygen supply-demand mismatch โ†’ ischaemia โ†’ myocardial necrosis (~20โ€“40 min for irreversible injury).
    • ๐Ÿงฉ STEMI: complete occlusion โ†’ transmural infarction; NSTEMI: partial occlusion โ†’ subendocardial infarction.
    • ๐Ÿงช Cellular changes: coagulative necrosis โ†’ neutrophilic infiltration โ†’ granulation tissue โ†’ fibrosis.
    • ๐Ÿซ€ Complications relate to infarct size, location, and residual LV function.
    โš ๏ธ Risk Factors
    • ๐Ÿšฌ Smoking
    • ๐Ÿ’‰ Hypertension, diabetes mellitus, dyslipidaemia
    • ๐Ÿ‘ด Age, male sex, family history of premature CAD
    • โš–๏ธ Obesity, sedentary lifestyle, poor diet
    • ๐Ÿ’Š Cocaine use or vasospastic disorders (Prinzmetal angina)
    ๐Ÿงฉ Clinical Features
    • ๐Ÿ’” Central chest pain: crushing, radiates to arm, neck, jaw; >20 min, not relieved by rest or GTN
    • ๐Ÿ˜ฐ Associated: sweating, nausea, vomiting, palpitations, dyspnoea, syncope
    • ๐Ÿฉบ Exam: tachy/bradycardia, hypotension, raised JVP, S3 gallop, pulmonary oedema
    • ๐Ÿ‘ต Elderly, diabetic, women: may present atypically (syncope, confusion, epigastric pain, silent MI)
    ๐Ÿ”Ž Differential Diagnosis
    • Unstable angina
    • Aortic dissection
    • Massive pulmonary embolism
    • Pericarditis
    • GORD or musculoskeletal chest pain
    ๐Ÿงช Investigations
    • ๐Ÿ“Š ECG: STEMI โ†’ ST elevation โ‰ฅ1 mm in โ‰ฅ2 limb leads or โ‰ฅ2 mm in chest leads ยฑ new LBBB; NSTEMI โ†’ ST depression/T inversion or non-specific changes
    • ๐Ÿงฌ Cardiac biomarkers: troponin I/T rises 4โ€“6h, peaks 12โ€“24h, normalises 7โ€“14 days
    • ๐Ÿงช Bloods: FBC, U&E, glucose, lipids, coagulation screen
    • ๐Ÿฉป CXR: pulmonary oedema, alternative causes
    • ๐Ÿฉบ Echocardiography: regional wall motion abnormalities, LV function, complications (VSD, MR, pericardial effusion)
    • Optional: Coronary angiography for diagnosis & PCI planning
    ๐Ÿš‘ Immediate & Ongoing Management of Acute MI (MONA-BASH + Long-Term Care)

    All recommendations are aligned with NICE NG185: Myocardial infarction: secondary prevention and NICE QS68: Acute coronary syndromes.

    • ๐Ÿ’Š Morphine + Metoclopramide โ€“ for severe pain and nausea; titrate carefully, monitor BP & respiration (NICE QS68, 2020)
    • ๐Ÿ’จ Oxygen โ€“ only if SpOโ‚‚ <94%; routine oxygen is not recommended in normoxaemic patients (NICE QS68, NG185)
    • ๐Ÿ’‰ Nitrates โ€“ GTN spray or infusion if BP adequate; relieve ischaemic pain, reduce preload (NG185 recommendation 1.4.7)
    • ๐Ÿฉธ Aspirin 300 mg PO stat โ†’ lifelong low-dose (75โ€“100 mg) unless contraindicated (NG185 1.5.1)
    • ๐Ÿ’™ Beta-blocker โ€“ if no contraindication, start early to reduce mortality, arrhythmia risk, and infarct size (NG185 1.5.2)
    • ๐Ÿฉบ ACE inhibitor / ARB โ€“ initiate within 24h (low dose, titrate); especially beneficial in anterior MI, LV dysfunction, diabetes, hypertension (NG185 1.5.3)
    • ๐ŸŸ  High-intensity statin โ€“ e.g., atorvastatin 80 mg; reduce recurrent MI, stabilise plaques (NG185 1.5.4)
    • ๐Ÿ’‰ Anticoagulation โ€“ unfractionated heparin or fondaparinux per protocol; adjust for renal function and bleeding risk (QS68 1.3.2)
    • ๐Ÿงฌ Reperfusion therapy โ€“ primary PCI if STEMI within 120 min; thrombolysis if delayed or unavailable (NG185 1.4.1โ€“1.4.3)
    • ๐Ÿ“ˆ Continuous monitoring โ€“ ECG telemetry for arrhythmias, vitals, urine output, fluid balance (QS68 1.2.1)
    • ๐Ÿฅ Early mobilisation โ€“ within 24h if stable, to prevent DVT, optimise recovery (NG185 1.6.1)
    • ๐Ÿซ€ Cardiac rehabilitation referral โ€“ exercise, education, psychosocial support (NG185 1.6.2, QS68 1.6)
    • ๐Ÿ’Š Dual antiplatelet therapy (DAPT) โ€“ aspirin + P2Yโ‚โ‚‚ inhibitor (clopidogrel/ticagrelor/prasugrel) for 12 months unless high bleeding risk (NG185 1.5.1โ€“1.5.2)
    • โš–๏ธ Risk factor optimisation โ€“ blood pressure, glycaemic management, weight loss, smoking cessation (NG185 1.7.1โ€“1.7.4)
    • ๐Ÿฉบ Follow-up & monitoring โ€“ outpatient cardiology review, echocardiography for LV function, ECG, lipid profile (NG185 1.6.3)
    • ๐Ÿง  Patient education โ€“ recognise angina, adherence to medications, lifestyle, emergency plan (NG185 1.6.2)
    • ๐Ÿ’” Psychosocial support โ€“ address anxiety/depression post-MI; refer to counselling or rehab psychologist if needed (NG185 1.6.2)
    ๐Ÿ“Š ACS Comparison โ€“ STEMI vs NSTEMI vs Unstable Angina
    Condition Key Features Management (NICE/UK)
    โšก STEMI
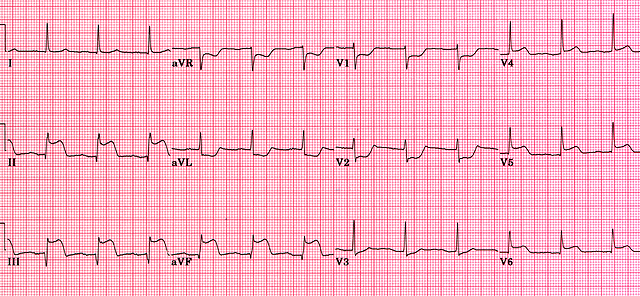
    • ECG: ST elevation โ‰ฅ2 contiguous leads or new LBBB
    • Troponin: elevated
    • Pathophysiology: complete coronary occlusion โ†’ transmural infarct
    • Immediate reperfusion: PCI โ‰ค120 min, thrombolysis if delayed
    • DAPT + anticoagulation, statin, ACEi, beta-blocker
    • Monitor for arrhythmia, heart failure, shock
    ๐Ÿ’” NSTEMI
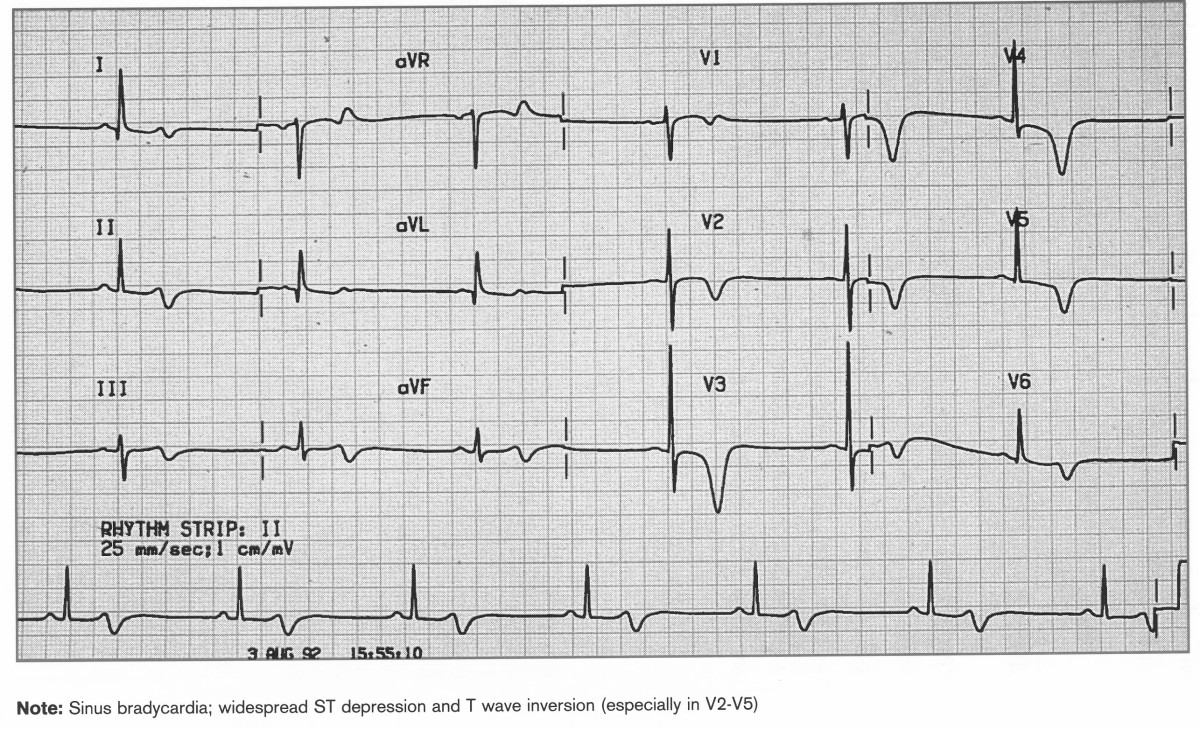
    • ECG: ST depression/T inversion, non-specific
    • Troponin: elevated
    • Partial/temporary occlusion โ†’ subendocardial infarct
    • Antiplatelets + anticoagulation
    • Early PCI (24โ€“72h) if high-risk
    • Secondary prevention: statin, ACEi, beta-blocker, lifestyle
    ๐Ÿ˜ฎโ€๐Ÿ’จ Unstable Angina
    • ECG: transient ST depression/T inversion, may be normal at rest
    • Troponin: normal
    • Critical ischaemia without infarction
    • Antiplatelets ยฑ anticoagulation
    • Anti-anginals (GTN, beta-blocker)
    • Early PCI/CABG if refractory/high-risk
    ๐Ÿ“Œ Post-ACS Complications โ€“ Diagnosis & Management
    Complication Diagnosis / Key Features Management (NICE / UK)
    ๐Ÿซ€ Heart Failure
    • Symptoms: breathlessness, orthopnoea, fatigue, oedema
    • Signs: raised JVP, basal crackles, S3 gallop
    • Investigations: BNP/NT-proBNP, ECG, CXR, echocardiography
    • Timing: early (acute) or late (chronic post-MI)
    • Diuretics for symptom relief
    • ACEi/ARB, beta-blocker, MRA for mortality
    • Fluid optimization, monitor electrolytes
    • Consider ICD/CRT if indicated
    โšก Arrhythmias
    • ECG: VT, VF, AF, bradyarrhythmias
    • Symptoms: palpitations, syncope, hypotension, cardiac arrest
    • Investigations: telemetry, electrolytes, echo
    • Timing: early (hoursโ€“days) or late (weeks)
    • Unstable VT/VF โ†’ DC cardioversion/defibrillation
    • AF โ†’ rate control ยฑ anticoagulation
    • Bradyarrhythmias โ†’ atropine ยฑ pacing
    • Correct reversible causes: electrolytes, ischaemia
    ๐Ÿฉธ Reinfarction / Recurrent Ischaemia
    • Chest pain recurrence, ECG changes
    • Troponin rise
    • Angiography: stent thrombosis or new lesion
    • Urgent PCI if indicated
    • Optimize DAPT
    • Manage risk factors: statin, ACEi, beta-blocker, lifestyle
    ๐Ÿซ€ Mechanical Complications
    • VSD โ†’ new murmur, shock
    • Papillary muscle rupture โ†’ acute MR, pulmonary oedema
    • Free wall rupture โ†’ hypotension, tamponade
    • Investigations: echo, haemodynamics
    • Urgent surgical repair
    • Stabilise: inotropes, vasopressors, IABP if needed
    • ICU monitoring
    ๐Ÿฉบ Pericarditis / Dresslerโ€™s
    • Chest pain (pleuritic), pericardial rub
    • ECG: widespread ST elevation, PR depression
    • Raised CRP/ESR, 1โ€“6 weeks post-MI
    • NSAIDs for inflammation/pain
    • Colchicine if recurrent
    • Monitor for pericardial effusion/tamponade
    ๐Ÿฉธ Bleeding (Antithrombotics)
    • Bruising, GI bleed, haematuria
    • Drop in Hb, hypotension
    • Review concurrent meds
    • Stop/adjust antithrombotics temporarily
    • Supportive care: fluids, transfusion if needed
    • Investigate source of bleeding
    ๐Ÿซ€ Revascularisation Strategies Post-ACS โ€“ PCI vs Stenting vs CABG
    โš ๏ธ Indication / Clinical Scenario ๐Ÿ› ๏ธ Revascularisation Strategy ๐Ÿ’Š Post-Procedure Management / NICE Guidance
    โšก STEMI within 120 min, suitable coronary anatomy Primary PCI with Drug-Eluting Stent (DES)
    • ๐Ÿฉบ Dual Antiplatelet Therapy (DAPT): aspirin + P2Y12 inhibitor for 12 months
    • ๐Ÿ’Š High-intensity statin, beta-blocker, ACE inhibitor
    • ๐Ÿ“ˆ Monitor for stent thrombosis (chest pain, ECG changes, troponin rise)
    • ๐Ÿƒ Cardiac rehabilitation & lifestyle modification
    ๐Ÿ’” NSTEMI with high-risk features (dynamic ECG changes, elevated troponin, haemodynamic instability) Early invasive PCI with DES (within 24โ€“72h)
    • ๐Ÿฉบ DAPT for 12 months
    • ๐Ÿ’Š Secondary prevention: statin, ACEi, beta-blocker, lifestyle changes
    • ๐Ÿ“ˆ Monitor for recurrent ischaemia, arrhythmias, heart failure
    ๐Ÿงฉ Multivessel disease, LV dysfunction, left main stenosis CABG (Coronary Artery Bypass Grafting)
    • โฑ๏ธ Timing: urgent if ongoing ischaemia/shock; elective 3โ€“7 days if stable
    • ๐Ÿ’Š Perioperative antiplatelet management: stop P2Y12 inhibitor 5โ€“7 days pre-op; continue aspirin
    • ๐Ÿฅ Post-CABG: secondary prevention (statin, ACEi, beta-blocker), cardiac rehab, lifestyle modification
    • ๐Ÿฉบ Monitor for graft patency, arrhythmias, heart failure
    โŒ Failed PCI or unsuitable coronary anatomy Elective / urgent CABG
    • ๐Ÿ’Š Optimise medical therapy before surgery
    • ๐Ÿฅ Post-op secondary prevention & rehab
    • ๐Ÿฉบ Close ICU / CCU monitoring for complications
    โš–๏ธ High bleeding risk or short DAPT requirement Bare-Metal Stent (BMS) during PCI
    • ๐Ÿฉบ Shortened DAPT (1 month) if bleeding risk > thrombosis risk
    • ๐Ÿ’Š Continue statin, ACEi, beta-blocker
    • ๐Ÿ“ˆ Monitor for restenosis; regular follow-up & lifestyle optimisation
    ๐Ÿ’ก Teaching Pearls

    ๐Ÿ”‘ ECG within 10 min of chest pain.
    โฑ๏ธ โ€œTime is muscleโ€ โ€“ early reperfusion saves myocardium.
    โš ๏ธ Elderly and diabetic patients may present atypically; maintain high suspicion.
    ๐Ÿฅ Discharge on secondary prevention: DAPT, beta-blocker, ACEi, statin, cardiac rehab.
    ๐Ÿงช Monitor for arrhythmias, heart failure, mechanical complications, pericarditis, and bleeding during hospital stay.


    Additional related clinical topics

    Acute Coronary Syndrome (ACS) NSTEMI USA โค๏ธ

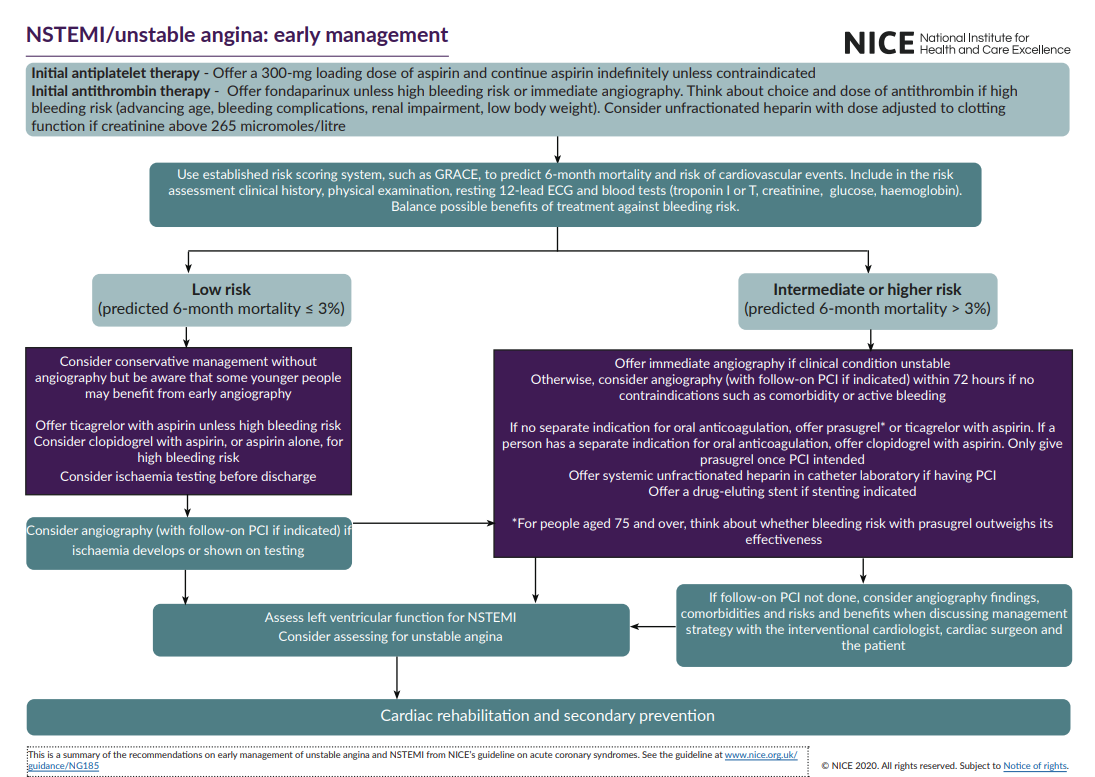
    ๐Ÿซ€ NSTEMI / Unstable Angina (NSTE-ACS) - Stepwise Management (NICE NG185 + ESC 2023)
    0๏ธโƒฃ Definitions (set expectations early)
    • NSTEMI: symptoms/signs of myocardial ischaemia + rise/fall in troponin (myocardial necrosis) without persistent ST elevation.
    • Unstable angina: ischaemic symptoms (often with ECG changes) but troponin not elevated.
    • Core goal: stabilise myocardium, prevent thrombus extension, and use risk-based angiography to reduce recurrent MI/death.
    1๏ธโƒฃ Recognition & Immediate Actions (first 10 minutes)
    • ๐ŸŽฏ Suspect with chest pain/pressure (or atypical dyspnoea/collapse) especially in older adults, women, diabetes, CKD.
    • ๐Ÿ“Š 12-lead ECG immediately; repeat if pain continues or ECG evolves (e.g., q15โ€“30 min early on).
    • ๐Ÿ“Ÿ Continuous cardiac monitoring/telemetry; defib available โšก.
    • ๐Ÿซ Oxygen only if hypoxaemic (target 94โ€“98%; 88โ€“92% if risk of hypercapnic failure).
    • ๐Ÿ’‰ IV access, baseline obs, NEWS2, point-of-care glucose.
    • ๐Ÿšซ Do not give DAPT before diagnosis is made (avoid bleeding harm in mimics like dissection/PE).
    2๏ธโƒฃ Investigations (do not delay treatment)
    • ๐Ÿงช Bloods: hs-troponin, FBC, U&E/creatinine, glucose, clotting, LFTs (optional), lipids (can be taken early for baseline).
    • โฑ๏ธ Serial troponin: use local hs-troponin pathway (often 0/1โ€“2 h). A dynamic rise/fall supports NSTEMI.
    • ๐Ÿ“ท CXR if alternative diagnosis suspected (pulmonary oedema, pneumothorax, infection) - do not โ€œroutine-delayโ€.
    • ๐Ÿซ€ Echocardiography: assess LV function (all NSTEMI) and look for complications (MR, regional wall motion abnormality, HF).
    • ๐Ÿ”Ž Consider mimics selectively: dissection (clinical red flags), PE, myocarditis/pericarditis (pleuritic pain, viral prodrome, diffuse ST changes).
    3๏ธโƒฃ Risk Stratification (NICE = GRACE 6-month mortality)
    • ๐Ÿ“Š Once NSTEMI/UA diagnosis made and aspirin + antithrombin offered, assess risk using a score predicting 6-month mortality (e.g. GRACE).
    • ๐ŸŸข Low risk: predicted 6-month mortality ≤3% โ†’ consider conservative strategy (no early angiography) if clinically stable.
    • ๐ŸŸ  Intermediate/high risk: predicted 6-month mortality >3% โ†’ usually benefit from angiography (timing below).
    • ๐Ÿšจ Unstable / very high-risk features: haemodynamic instability, cardiogenic shock, refractory/recurrent ischaemia, malignant arrhythmia (VT/VF), acute HF/pulmonary oedema โ†’ immediate angiography.
    4๏ธโƒฃ Immediate Medical Therapy (anti-ischaemic + antithrombotic)
    • ๐Ÿ’Š Aspirin: 300 mg loading then continue indefinitely unless contraindicated.
    • ๐Ÿ’‰ Antithrombin (NICE):
      • Fondaparinux 2.5 mg SC daily unless immediate angiography is planned, or bleeding risk is very high.
      • Significant renal impairment (creatinine >265 micromol/L): consider unfractionated heparin (UFH) instead, dose-adjusted to clotting monitoring.
      • โš ๏ธ High bleeding risk: individualise agent/dose (age, prior bleeding, renal impairment, low body weight).
    • ๐ŸŒฌ๏ธ Nitrates: GTN SL/IV for ongoing ischaemic pain and hypertension if no contraindications (avoid in hypotension, severe AS, suspected RV infarct, recent PDE5 inhibitor).
    • ๐Ÿ’‰ Analgesia: IV opioid titrated to pain + antiemetic if needed.
    • ๐Ÿซ€ Beta-blocker: consider early oral beta-blocker if tachycardic/hypertensive and no acute HF/shock/bradycardia/heart block/asthma exacerbation.
    • ๐Ÿงด High-intensity statin: start early unless contraindicated (dose per local post-ACS pathway).
    5๏ธโƒฃ P2Y12 inhibitor strategy (NICE NG185 - depends on angiography/PCI plan)
    • If coronary angiography is planned:
      • If no separate indication for ongoing oral anticoagulation: offer prasugrel or ticagrelor with aspirin.
        • Prasugrel: only give once coronary anatomy is defined and PCI is intended (and weigh bleeding risk carefully, especially age โ‰ฅ75).
      • If a person does have a separate indication for ongoing oral anticoagulation: offer clopidogrel with aspirin.
    • If PCI is not indicated (conservative management):
      • Offer ticagrelor + aspirin unless high bleeding risk.
      • If high bleeding risk: consider clopidogrel + aspirin or aspirin alone.
    6๏ธโƒฃ Invasive strategy & timing (NICE)
    • ๐Ÿš‘ Immediate angiography if clinical condition is unstable (shock, refractory ischaemia, life-threatening arrhythmia, acute HF).
    • ๐Ÿ•’ Otherwise, consider angiography (with follow-on PCI if indicated) within 72 hours if no contraindications (e.g., severe comorbidity, active bleeding).
    • ๐Ÿฉป PCI practicals (NICE): if PCI performed, offer systemic UFH in the cath lab whether or not fondaparinux has already been given.
    • ๐Ÿงท If stenting indicated, offer a drug-eluting stent.
    • ๐Ÿ” If revascularisation strategy unclear (PCI vs CABG), discuss in a heart-team format (interventional cardiology + cardiac surgery) with the patient.
    7๏ธโƒฃ Supportive care & complication surveillance
    • ๐Ÿ›๏ธ Monitored bed until stable; watch for VT/VF, AF, heart block, recurrent ischaemia.
    • ๐ŸŒŠ Treat HF/pulmonary oedema promptly (diuretics, NIV/oxygen if hypoxaemic, specialist input).
    • ๐Ÿงช Glucose: keep blood glucose <11 mmol/L while avoiding hypoglycaemia; consider dose-adjusted insulin infusion early if needed.
    • ๐Ÿฉธ Bleeding prevention: review anticoagulants/NSAIDs, consider gastroprotection if high GI bleed risk (local policy).
    • ๐Ÿง  Always re-check diagnosis if pain is tearing/back, neuro deficit, pulse deficit, or mediastinal widening โ†’ think dissection (avoid antithrombotics until excluded).
    8๏ธโƒฃ Before discharge (NICE)
    • ๐Ÿซ€ Assess LV function in all NSTEMI patients and document in discharge summary.
    • ๐Ÿงช If managed conservatively without angiography: consider ischaemia testing before discharge to quantify inducible ischaemia.
    • ๐Ÿ“‹ Clear plan for antithrombotics, BP, lipids, diabetes control, and follow-up.
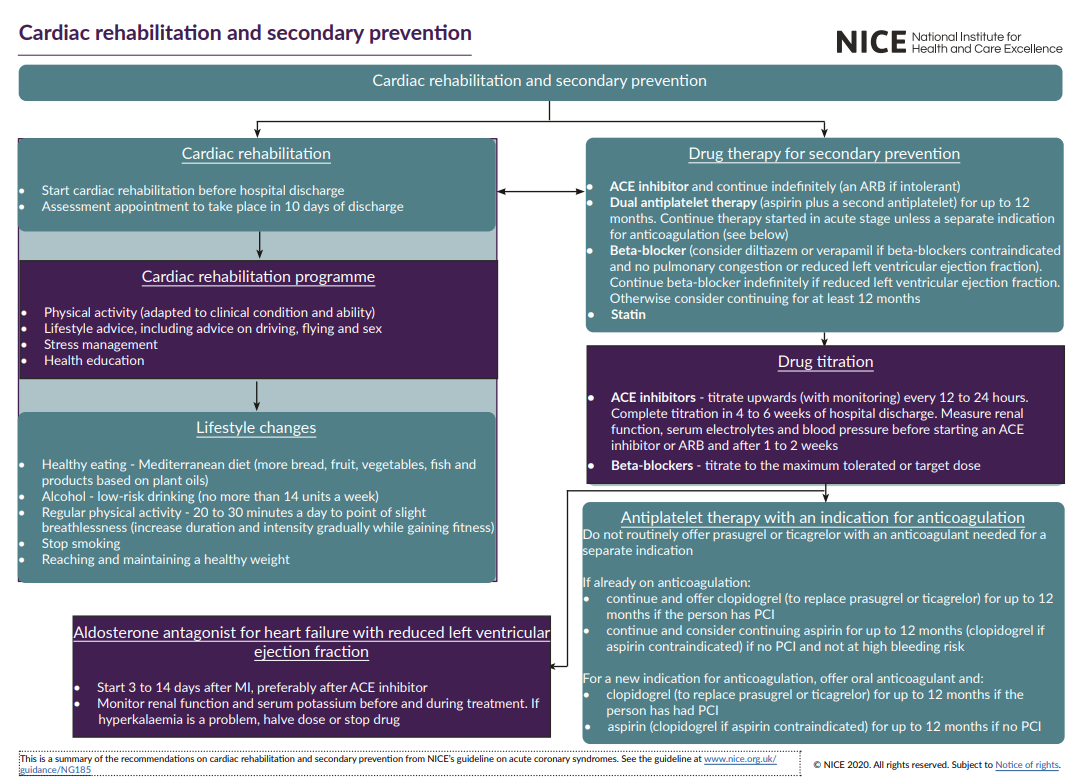
    9๏ธโƒฃ Secondary prevention (long-term survival gains)
    • ๐Ÿ’Š DAPT: aspirin + selected P2Y12 inhibitor typically for up to 12 months (shorter if bleeding risk high; longer only if specialist-directed).
    • ๐Ÿงด Statin: high-intensity long-term; consider add-on lipid therapy in very high risk if not at goal (specialist pathway).
    • ๐Ÿ’Š ACE inhibitor: start once haemodynamically stable and continue indefinitely after MI; titrate to target/max tolerated.
    • ๐Ÿซ€ Beta-blocker: especially if LV dysfunction/HF; individualise if preserved EF.
    • ๐Ÿงช MRA (eplerenone): consider if LVEF โ‰ค40% with HF or diabetes (monitor K+ and renal function).
    • ๐Ÿฅ Cardiac rehabilitation referral + lifestyle: smoking cessation ๐Ÿšญ, Mediterranean diet ๐Ÿฅ—, graded exercise ๐Ÿƒโ€โ™‚๏ธ, weight/BP optimisation.
    ๐Ÿ“Š Risk Scores Quick Links
    ๐Ÿ–ผ๏ธ Illustrations
    NSTEMI ECG NICE/ACC ACS Algorithm Secondary Prevention

    ๐Ÿ’ก Teaching Pearl: NSTE-ACS is risk-based medicine.
    ๐Ÿ”น Unstable physiology โ†’ immediate cath lab.
    ๐Ÿ”น Stable but >3% 6-month mortality (GRACE) โ†’ angiography within 72 hours.
    ๐Ÿ”น Low risk (โ‰ค3%) โ†’ conservative strategy is reasonable, but ensure LV function assessment and appropriate ischaemia testing/follow-up.

    ๐Ÿ“š References (guidelines)

    Acute Coronary Syndrome (ACS) STEMI โค๏ธ

    ๐Ÿ“Š Initial Management of Acute STEMI
    ๐Ÿซ€ STEMI Management (NICE NG185-aligned summary)
    ๐Ÿš‘ Immediate (do in parallel)
    • ABCDE, call for senior help/cath-lab pathway early; treat as time-critical.
    • 12-lead ECG within minutes + repeat if evolving; continuous cardiac monitoring.
    • IV access x2, bloods (incl. troponin, FBC, U&E, clotting) but do not delay reperfusion.
    • Oxygen: only if hypoxaemic. Target 94โ€“98% (or 88โ€“92% if risk of hypercapnic respiratory failure).
    • Analgesia: IV opioid (morphine/diamorphine) + antiemetic if needed.
    • GTN: for ongoing ischaemic pain and hypertension if no contraindications (avoid if hypotension, suspected RV infarct, severe aortic stenosis, recent PDE5 inhibitor use).
    ๐Ÿ’Š Antiplatelet therapy
    • Aspirin: give 300 mg loading ASAP, then continue long-term unless contraindicated.
    • If primary PCI planned:
      • Prasugrel + aspirin (if not already taking an oral anticoagulant).
      • If age ≥75 or bleeding risk high: consider whether prasugrel risk outweighs benefit; use ticagrelor or clopidogrel instead.
      • If already on an oral anticoagulant: use clopidogrel + aspirin.
    • If STEMI not treated with PCI: offer ticagrelor + aspirin unless high bleeding risk (then consider clopidogrel + aspirin or aspirin alone).
    ๐Ÿงฌ Antithrombin / anticoagulation (NICE specifies by strategy)
    • Primary PCI (radial access preferred): offer unfractionated heparin with bailout glycoprotein IIb/IIIa inhibitor (not routine upfront).
    • If femoral access needed: consider bivalirudin with bailout glycoprotein IIb/IIIa inhibitor.
    • If fibrinolysis given: give an antithrombin at the same time (agent per local protocol).
    • Do not give routine GP IIb/IIIa inhibitors or fibrinolytics before arrival at cath lab if primary PCI planned.
    โšก Reperfusion strategy (key NICE timing)
    • Primary PCI (preferred): offer if presenting within 12 hours of symptom onset and PCI can be delivered within 120 minutes of the time when fibrinolysis could have been given.
    • Fibrinolysis: offer if within 12 hours and primary PCI cannot be delivered within that 120-minute window.
    • Late presenters: consider angiography ยฑ PCI if presenting >12 hours with ongoing ischaemia or cardiogenic shock.
    ๐Ÿฉป If fibrinolysis is used (what to do next)
    • Give an antithrombin at the same time.
    • Repeat ECG at 60โ€“90 minutes.
    • If failed reperfusion (residual ST elevation): offer immediate coronary angiography with follow-on PCI if indicated; do not repeat fibrinolysis.
    • If recurrent ischaemia after fibrinolysis: seek urgent cardiology advice and consider angiography/PCI.
    • If clinically stable after successful fibrinolysis: consider angiography during the same admission.
    ๐Ÿฅ In-lab / early inpatient priorities
    • Radial access preferred over femoral where feasible.
    • If stenting indicated: offer a drug-eluting stent.
    • If multivessel disease and no shock: offer complete revascularisation (often during index admission). If cardiogenic shock: consider culprit-only during the index procedure.
    • Assess left ventricular function in all STEMI patients (echo before discharge or early after).
    ๐Ÿ“ฆ Post-PCI / Discharge (secondary prevention package)
    • DAPT: continue dual antiplatelet therapy as directed by cardiology (commonly up to 12 months, shorter if bleeding risk high).
    • High-intensity statin: e.g. atorvastatin (local pathway often uses high dose after MI).
    • ACEi/ARB: start when haemodynamically stable; particularly important if LV dysfunction/anterior MI/diabetes.
    • Beta-blocker: offer especially if LV dysfunction/heart failure; many UK pathways continue for at least 12 months even without LV dysfunction (individualise).
    • Aldosterone antagonist (e.g., eplerenone): consider if LV dysfunction with heart failure or diabetes after MI (specialist-led, monitor K+ and renal function).
    • Cardiac rehab: referral for structured rehab + education.
    • Lifestyle: smoking cessation ๐Ÿšญ, Mediterranean-style diet ๐Ÿฅ—, graded exercise ๐Ÿƒโ€โ™‚๏ธ, weight and BP optimisation, vaccination advice per local policy.
    ๐Ÿ“Š Risk / follow-up (use the right tools)
    • STEMI reperfusion decisions are time/ECG-driven; formal risk scores are more central to NSTEMI/UA pathways (e.g., GRACE).
    • After STEMI, prognosis and therapy intensity are guided by LVEF, complications (arrhythmia/HF), residual ischaemia, bleeding risk, and completeness of revascularisation.

    NICE sources: NG185 recommendations | NG185 STEMI visual summary (PDF)

    Site of Coronary Artery Occlusion in STEMI
    1. Right coronary artery occlusion
      • ST depression in lead I
      • ST elevation in lead III greater than in lead II
      a. Proximal occlusion
      • ST elevation more than 1 mm with positive T wave in lead Vโ‚„R
      b. Distal occlusion
      • ST isoelectric with a positive T wave in lead Vโ‚„R
    2. Left circumflex artery occlusion
      • ST elevation in lead II greater than lead III
      • ST isoelectric or elevated in lead I
      • ST isoelectric or depressed with negative T wave in Vโ‚„R
      a. Extension to posterior wall
      • ST depression in precordial leads
      b. Extension to lateral wall
      • ST elevation in leads I, aVL, Vโ‚…, and Vโ‚†
    3. Left anterior descending artery occlusion
      a. Proximal to first septal branch and first diagonal branch
      • ST elevation in leads aVR and aVL
      • ST depression in leads II, III, and aVF
      • ST elevation in lead Vโ‚ (> 2 mm) and leads Vโ‚‚ to Vโ‚„
      • ST isoelectric or depressed in leads Vโ‚… and Vโ‚†
      • Acquired intra-Hisian or RBBB may occur
      b. Distal to first septal branch, proximal to first diagonal branch
      • ST elevation in lead I and aVL
      • ST depression in lead III (lead II is isoelectric)
      • ST elevation in leads Vโ‚‚ to Vโ‚† but not in lead Vโ‚
      c. Distal to first diagonal branch, proximal to first septal branch
      • ST depression in lead aVL, highest in lead III
      • ST elevation in inferior leads, highest in lead III
      • ST elevation in leads Vโ‚ to Vโ‚„
      d. Distal LAD
      • ST depression in aVR
      • ST elevation in inferior leads, highest in lead II
      • ST elevation in leads Vโ‚ƒ to Vโ‚†
    4. Left main coronary artery occlusion
      • ST elevation in lead aVR
      • ST elevation in lead Vโ‚ (lower than that of lead aVR)
      • ST depression in leads II and aVF
      • ST depression in the precordial leads to the left of Vโ‚‚
    The ECG + Chest Pain or can be silent is diagnostic
    ๐Ÿซ€ Management of Acute STEMI (Chest Pain + ECG) - NICE NG185 + ESC 2023 aligned

    ๐Ÿšจ Key principle: STEMI is a time-critical reperfusion emergency. Do not delay reperfusion for CXR, routine bloods, or waiting for troponin.
    NICE timing logic: offer primary PCI if it can be delivered within 120 minutes of the time fibrinolysis could have been given; otherwise offer fibrinolysis (if within 12 hours and no contraindications).
    Time = myocardium โฑ๏ธ

    โšก Pathophysiology (why speed matters)
    • Cause: usually plaque rupture/erosion โ†’ platelet activation + thrombin โ†’ acute coronary thrombotic occlusion.
    • Wavefront necrosis: infarction spreads from endocardium โ†’ epicardium over hours; early reperfusion salvages myocardium and preserves LV function.
    • Electrical instability: ischaemia triggers VT/VF risk early; hence monitoring and defib readiness.
    ๐Ÿฉบ Clinical features (typical + atypical)
    • Typical pain: central crushing/tight chest pain >20 min ยฑ radiation to jaw/left arm/neck/back.
    • Associated symptoms: dyspnoea, diaphoresis ๐Ÿ˜ฐ, nausea/vomiting, palpitations, syncope, sense of doom.
    • Atypical presentations: older adults, women, diabetes, CKD: dyspnoea, collapse, epigastric discomfort, confusion.
    • Examination clues: hypotension/shock, pulmonary oedema, new pansystolic murmur (papillary muscle rupture), bradycardia (inferior/RV MI), arrhythmia.
    ๐Ÿ“‰ ECG diagnosis (STEMI + STEMI equivalents)
    • ST elevation in โ‰ฅ2 contiguous leads:
      • V2โ€“V3: โ‰ฅ2 mm (men) or โ‰ฅ1.5 mm (women)
      • Other leads: โ‰ฅ1 mm
    • Posterior MI: ST depression V1โ€“V3 with tall R waves โ†’ record V7โ€“V9 (posterior ST elevation supports STEMI pathway).
    • Right ventricular MI: consider with inferior STEMI + hypotension โ†’ record V3R/V4R (avoid nitrates if RV infarct suspected).
    • LBBB: new/presumed new LBBB with ischaemic symptoms is high risk; use clinical picture + ECG criteria (e.g., concordant changes) and act early if STEMI suspected.
    • Repeat ECGs: if symptoms persist or evolve (dynamic STEMI can be missed on first trace).
    ๐Ÿงช Troponin (do not wait for it)
    • Troponin supports diagnosis and risk, but STEMI is a clinical + ECG diagnosis requiring immediate action.
    • High-sensitivity troponin typically rises within hours; repeating at 3 hours is useful when ECG is non-diagnostic.
    • Bedside echo can help if diagnosis unclear (regional wall motion abnormality), but should not delay reperfusion when STEMI is clear.
    ๐Ÿš‘ Immediate actions (first 5โ€“10 minutes)
    • ABCDE, call cath lab / STEMI pathway early; senior decision-maker involved early.
    • Cardiac monitor + defib ready โšก; treat VT/VF per ALS.
    • 12-lead ECG and repeat if evolving; consider posterior/right-sided leads when indicated.
    • IV access x2; point-of-care glucose; bloods (FBC, U&E, clotting, troponin) but do not delay reperfusion.
    • Oxygen only if hypoxaemic: target 94โ€“98% (or 88โ€“92% if risk of hypercapnic respiratory failure).
    • Do not delay reperfusion for CXR unless you strongly suspect dissection/other alternative diagnosis needing immediate imaging.
    ๐Ÿ’Š Symptom relief (analgesia + anti-ischaemic)
    • Opioid analgesia: IV morphine/diamorphine titrated to pain, plus antiemetic (e.g., metoclopramide/ondansetron) as needed.
    • GTN (sublingual or IV) for ongoing pain and hypertension if no contraindications:
      • Avoid in hypotension, suspected RV infarct, severe aortic stenosis, or recent PDE5 inhibitor use.
    • Positioning: upright if pulmonary oedema; supine/legs elevated if hypotensive (and treat shock protocol).
    ๐Ÿฉธ Antiplatelet therapy (NICE NG185)

    โœ… Core: Aspirin + a P2Y12 inhibitor (dual antiplatelet therapy, DAPT).
    NICE specifies prasugrel + aspirin as the preferred option for STEMI undergoing primary PCI in those not on an oral anticoagulant, with age/bleeding cautions.

    • Aspirin: 300 mg loading ASAP (chewed/crushed if needed), then 75 mg daily long-term unless contraindicated.
    • If primary PCI planned (and not on an oral anticoagulant): offer prasugrel + aspirin.
      • Prasugrel cautions: avoid if prior stroke/TIA; consider alternatives if age โ‰ฅ75 or weight <60 kg (bleeding risk).
      • If bleeding risk outweighs benefit (often โ‰ฅ75): offer ticagrelor or clopidogrel instead (with aspirin).
    • If already taking an oral anticoagulant: offer clopidogrel + aspirin (avoid prasugrel/ticagrelor in this setting per NICE pathway).
    • If STEMI not treated with primary PCI (including after fibrinolysis): NICE supports ticagrelor + aspirin unless bleeding risk high (then consider clopidogrel + aspirin).
    ๐Ÿงฌ Antithrombin / anticoagulation (match to strategy - NICE NG185)
    • Primary PCI with radial access: offer unfractionated heparin (UFH) with bailout glycoprotein IIb/IIIa inhibitor (not routine upfront).
    • If femoral access needed: consider bivalirudin with bailout glycoprotein IIb/IIIa inhibitor.
    • If fibrinolysis is given: give an antithrombin at the same time (agent per local protocol).
    • Avoid routine pre-hospital fibrinolysis or routine GP IIb/IIIa inhibitor use when primary PCI is planned.
    • Renal function: adjust dosing where relevant and monitor bleeding risk closely.
    โšก Reperfusion strategy (NICE NG185 + ESC 2023 framing)
    • Primary PCI (preferred): offer coronary angiography with follow-on primary PCI if indicated when:
      • presentation is within 12 hours of symptom onset, and
      • primary PCI can be delivered within 120 minutes of the time fibrinolysis could have been given.
    • Fibrinolysis: offer if within 12 hours and timely primary PCI (as above) is not achievable and no contraindications.
    • Cardiogenic shock: offer urgent coronary angiography with follow-on PCI if indicated (within 12 hours; and consider even later if ongoing ischaemia/shock).
    • Late presenters (>12 hours): consider angiography/PCI if ongoing ischaemia, haemodynamic instability, malignant arrhythmias, or shock.
    • ESC practical emphasis: bypass non-PCI centres where possible; move directly to cath lab in confirmed STEMI to reduce system delay.
    ๐Ÿ’‰ If fibrinolysis is used (what to do next - NICE)
    • Give antithrombin at the same time as fibrinolysis.
    • Repeat ECG at 60โ€“90 minutes after fibrinolysis.
    • Failed reperfusion (e.g., persistent ST elevation): offer immediate coronary angiography with follow-on PCI if indicated; do not repeat fibrinolysis.
    • Recurrent ischaemia after fibrinolysis: seek urgent cardiology advice and consider angiography/PCI.
    • If clinically stable after successful fibrinolysis: consider angiography during the same admission.
    ๐Ÿฉป Cath lab / in-hospital strategy (NICE NG185)
    • Access: radial preferred when feasible (lower bleeding/vascular complications).
    • Stent choice: offer drug-eluting stent if stenting is indicated.
    • Multivessel disease:
      • If no shock: offer complete revascularisation (often during index admission; may be staged).
      • If cardiogenic shock: consider culprit-only revascularisation during index procedure.
    • LV function: assess LV function in all STEMI patients (echo before discharge or early follow-up).
    ๐Ÿง  Special situations (high yield)
    • Inferior STEMI + hypotension: think RV infarct; record right-sided leads; avoid nitrates; treat with cautious fluids and urgent reperfusion.
    • Posterior MI: record V7โ€“V9; treat as STEMI equivalent if posterior ST elevation present.
    • Cardiac arrest with ROSC: if ECG/clinical picture suggests acute coronary occlusion, urgent cath lab discussion is warranted (local network protocol).
    • Suspected aortic dissection: tearing pain radiating to back, pulse/BP differential, new AR murmur, mediastinal widening - avoid anticoagulants/thrombolysis and image urgently.
    ๐Ÿ’“ Beta-blockers, ACEi/ARB, MRA (inpatient + discharge)
    • ACEi/ARB: start when haemodynamically stable, especially with LV dysfunction, anterior MI, diabetes, or hypertension; titrate to target doses.
    • Beta-blocker: offer particularly if LV dysfunction or heart failure; avoid/withhold in shock, acute pulmonary oedema, severe bradycardia/heart block, or severe asthma.
    • Aldosterone antagonist (eplerenone): consider if LVEF โ‰ค40% with heart failure or diabetes after MI (monitor K+ and renal function closely).
    • High-intensity statin: start early unless contraindicated (dose per local post-MI pathway).
    ๐Ÿฉน Secondary prevention (what saves lives long-term)
    • DAPT: aspirin + P2Y12 inhibitor as directed (often up to 12 months; shorter if bleeding risk high; longer in selected high-ischaemic-risk cases - specialist decision).
    • Statin: high-intensity statin long-term; consider add-on lipid therapy in very high risk if targets not met (cardiology/lipid clinic pathway).
    • BP, diabetes, smoking: aggressive risk factor control (smoking cessation has one of the biggest absolute benefits).
    • Cardiac rehab: structured rehab improves outcomes and adherence; include exercise prescription, education, psychosocial support.
    • Vaccination: influenza (and other vaccinations per risk group policy) to reduce infection-triggered events.
    ๐Ÿ“… Inpatient monitoring and complications to watch for
    • Arrhythmias: VT/VF early; AF; bradyarrhythmias (inferior MI); monitor and treat per ALS/cardiology.
    • Heart failure / pulmonary oedema: diuretics, nitrates (if BP allows), ventilatory support as needed; assess LVEF.
    • Mechanical complications (2โ€“7 days): papillary muscle rupture (acute MR), VSD, free wall rupture (tamponade); suspect if sudden shock/new murmur.
    • Pericarditis: pleuritic pain, pericardial rub (early); Dressler syndrome later.
    ๐Ÿ“Š โ€œRisk stratificationโ€ (use the right tools)
    • Reperfusion decisions in STEMI are ECG + time + clinical status driven (not GRACE/TIMI).
    • After reperfusion, prognosis is guided by:
      • Killip class / heart failure severity
      • LVEF (echo)
      • Extent of coronary disease and success of revascularisation
      • Bleeding risk, renal function, frailty, and complications during admission
    • GRACE is primarily a NSTEMI/UA risk tool and is not the main determinant for acute STEMI reperfusion.

    ๐Ÿ’ก Teaching pearl: A โ€œnormalโ€ early troponin and a โ€œnormalโ€ early CT head/chest X-ray do not exclude STEMI. The life-saving decision is whether the ECG/clinical picture demands immediate reperfusion.

    ๐Ÿ“š References (guidelines)

    Secondary prevention Post Acute Coronary Syndrome

    ๐Ÿซ€ Secondary Prevention Post-ACS / IHD

    Secondary prevention aims to reduce recurrent cardiovascular events and improve long-term survival. It should be initiated prior to discharge.

    ๐Ÿ“‹ Prior to Discharge โ€“ Risk Assessment
    • Assess LVEF, residual ischaemia, completeness of revascularisation.
    • Check risk markers: LDL-C, HDL-C, triglycerides, fasting glucose, renal function.
    • โš ๏ธ LDL-C should be measured on admission (levels may fall post-ACS).
    ๐Ÿ’Š Antithrombotic Therapy
    • Dual Antiplatelet Therapy (DAPT): Aspirin (75โ€“100 mg OD) + P2Y12 inhibitor (e.g. ticagrelor, prasugrel, or clopidogrel). Continue โ‰ฅ12 months if low bleeding risk.
    • Triple Therapy: For AF / prosthetic valves: triple therapy โ‰ค1 week, then anticoagulant + single antiplatelet up to 12 months.
    • After 12 months โ†’ usually aspirin monotherapy.
    ๐Ÿฉธ Anticoagulation (selected cases)
    • AF with CHA2DS2-VASc โ‰ฅ2 โ†’ anticoagulant ยฑ antiplatelet (guided by bleeding risk).
    • LV thrombus post-MI โ†’ LMWH bridging to warfarin (or DOAC if appropriate).
    • Prolonged immobility post-MI โ†’ LMWH prophylaxis.
    ๐Ÿงฌ Lipid Management
    • LDL-C target: <1.4 mmol/L and โ‰ฅ50% reduction from baseline.
    • Statins: High-dose (Atorvastatin 80 mg nocte). Proven mortality reduction post-ACS.
    • Consider ezetimibe or PCSK9 inhibitor if LDL-C target not achieved.
    ๐Ÿ’Š Key Medications
    • Beta-blockers: Indicated if LVEF โ‰ค40% (Class I, LOE A).
    • ACE inhibitors: Ramipril 2.5 mg โ†’ titrate to 10 mg daily. If intolerant โ†’ ARB (valsartan/losartan).
    • Aldosterone antagonist: Eplerenone 25 mg OD in STEMI + LVEF โ‰ค40% with DM or HF symptoms.
    • Polypill strategy: Fixed-dose combinations may improve adherence.
    ๐Ÿšญ Lifestyle & Risk Modification
    • Smoking cessation: Offer NRT, varenicline/bupropion if appropriate. Refer to NHS stop-smoking services.
    • Diet: Mediterranean diet (fish, nuts, 5-a-day, low sat fat, โ†‘ soluble fibre).
    • Exercise: Mobilise early; target 150 min/week moderate intensity. Enrol in cardiac rehabilitation.
    ๐Ÿ“Š Quick Summary Table
    Drug / StrategyIndicationNotes
    ๐Ÿฉธ DAPTAll ACS patients unless contraindicatedAspirin + P2Y12 inhibitor โ‰ฅ12 months
    ๐Ÿ’Š AnticoagulationAF, LV thrombus, prosthetic valvesTriple โ‰ค1 week โ†’ OAC + SAPT
    ๐Ÿงฌ StatinsAll post-ACSAtorvastatin 80 mg nocte; LDL-C <1.4 mmol/L
    โค๏ธ Beta-blockersLVEF โ‰ค40%Reduce mortality & arrhythmia
    ๐Ÿ’Š ACEI/ARBLVEF <40%, DM, HTN, CKDTitrate to max tolerated dose
    ๐Ÿ’Š EplerenonePost-STEMI, LVEF โ‰ค40% + DM/HFMonitor Kโบ and renal function
    ๐Ÿšญ LifestyleAll patientsStop smoking, Mediterranean diet, cardiac rehab

    ๐Ÿ’ก Exam tip: Post-ACS secondary prevention is about โ€œDrugs + Lifestyle + Rehabโ€. Always mention cardiac rehabilitation and HCC surveillance in cirrhotics.

    Acute Coronary Syndrome (ACS): Complications

    โšก Arrhythmias
    • โค๏ธโ€๐Ÿ”ฅ Ventricular tachycardia: Often seen acutely during ischaemia or infarction. Treat persistent VT with IV amiodarone or lidocaine according to local/ALS guidance. Correct potassium and magnesium. Use synchronised DC cardioversion if haemodynamically compromised.
    • ๐Ÿ’“ Accelerated idioventricular rhythm: Wide-complex regular rhythm, usually rate <120/min. Often stable and may be a sign of reperfusion. Correct potassium and magnesium. Usually settles without treatment.
    • ๐Ÿšจ Ventricular fibrillation: Usually occurs early after MI and requires immediate defibrillation. Early VF does not always imply long-term ICD need, but VF after the first 24โ€“48 hours is more concerning. Start beta-blockade if not contraindicated and seek cardiology advice for late or recurrent arrhythmias.
    • ๐Ÿซ€ Atrial fibrillation: Not uncommon after ACS. Treat rate/rhythm depending on haemodynamic status, LV function and symptoms. Options include beta-blocker, digoxin or amiodarone depending on context. Consider anticoagulation according to stroke and bleeding risk.
    • ๐Ÿข Sinus bradycardia: Common with inferior MI. Withhold beta-blockers if significant bradycardia or hypotension. Give atropine if symptomatic. Consider temporary pacing if persistent compromise.
    • โ›” Third-degree AV block: Consider atropine, external pacing and urgent cardiology review. Temporary pacing may be needed, especially if haemodynamic compromise persists. A permanent pacemaker may be required if block does not resolve.
    • โš ๏ธ Second-degree AV block: Mobitz II or 2:1 / 3:1 block is more concerning than Wenckebach and may progress to complete heart block. Seek cardiology advice; temporary pacing may be required.
    • ๐ŸŸก First-degree AV block: Often needs no treatment. If associated with new bundle branch block or anterior MI, it may suggest more extensive conduction-system disease and requires close monitoring.
    ๐Ÿฉธ Thromboembolic Complications
    • ๐Ÿง  Systemic embolism: LV thrombus or atrial fibrillation may lead to embolic stroke or peripheral embolism. Risk is higher after large anterior MI and severe LV impairment. Consider echocardiography and anticoagulation where indicated.
    • ๐Ÿซ DVT and pulmonary embolism: Immobility, inflammation and acute illness increase venous thromboembolism risk. Use VTE assessment and thromboprophylaxis according to local policy, balancing bleeding risk and antiplatelet/anticoagulant therapy.
    ๐Ÿ— Structural Complications
    • ๐Ÿ’ฅ Free wall rupture: Rupture into the pericardium can cause tamponade, pulseless electrical activity and sudden death. Classically occurs several days after a large transmural MI as necrotic myocardium softens.
    • ๐ŸŒŠ Severe LV dysfunction / pump failure: Loss of viable myocardium may cause pulmonary oedema and cardiogenic shock. Treat pulmonary oedema with oxygen, nitrates if blood pressure allows, IV diuretics and urgent senior/cardiology input.
    • ๐Ÿซ€ Papillary muscle rupture: Presents with acute breathlessness, pulmonary oedema and a new loud pansystolic murmur from acute severe mitral regurgitation. Confirm with urgent echocardiography. Needs urgent cardiac surgical assessment.
    • ๐Ÿงฑ Ventricular septal rupture: Presents with acute heart failure, shock and a new harsh pansystolic murmur. Confirm with urgent echocardiography. Requires urgent cardiology/cardiac surgery input.
    • ๐Ÿ” Ventricular remodelling: Harmful thinning and dilatation after a large transmural MI. ACE inhibitors/ARBs, beta-blockers and mineralocorticoid receptor antagonists where indicated reduce adverse remodelling.
    • โžก๏ธ Right ventricular MI: Suspect with inferior STEMI, hypotension, raised JVP and clear lung fields. Check right-sided ECG leads, especially V4R. Avoid excessive nitrates/diuretics; cautious fluid loading may improve RV filling.
    ๐Ÿ” Recurrent Ischaemia and Reinfarction
    • ๐Ÿšจ Reinfarction: Suspect if recurrent chest pain, new ECG changes, haemodynamic deterioration or recurrent troponin rise. Discuss urgently with cardiology for repeat angiography/PCI or reperfusion strategy.
    • โžก๏ธ Right ventricular infarction: Presents with hypotension, raised JVP and clear lung fields, usually with inferior MI. ECG may show ST elevation in V4R. Echo is useful. Treat hypotension with cautious fluids and avoid preload-reducing drugs if unstable.
    ๐Ÿ”ฅ Inflammatory Complications
    • ๐Ÿซ€ Early post-MI pericarditis: Usually occurs within the first few days. Chest pain may be sharp, pleuritic or positional. Avoid routine NSAIDs early after MI unless specialist advice supports use; analgesia and cardiology guidance may be needed.
    • ๐Ÿ›ก Dresslerโ€™s syndrome: Immune-mediated pericarditis occurring weeks to months after MI. Features include fever, pleuritic chest pain and pericardial effusion. Treat with anti-inflammatory therapy under specialist guidance.
    ๐Ÿง  Psychological Complications
    • ๐Ÿ˜Ÿ Anxiety and depression: Common after ACS and may reduce quality of life, medication adherence and cardiac rehabilitation engagement.
    • ๐Ÿ’ฌ Ask about mood, sleep, fear of exertion, return to work, sexual activity and confidence after discharge.
    • ๐Ÿƒ Cardiac rehabilitation improves physical recovery, education, confidence and psychological adjustment.
    ๐Ÿ“ Exam Pearls
    • ๐Ÿšจ Early VF after MI needs defibrillation; late VF is more concerning for ongoing scar/ischaemia risk.
    • ๐Ÿข Inferior MI commonly causes bradycardia and AV block.
    • ๐Ÿ’ฅ New murmur plus pulmonary oedema after MI = think papillary muscle rupture or VSD.
    • โžก๏ธ Inferior MI + hypotension + raised JVP + clear lungs = right ventricular infarction.
    • ๐Ÿซ€ Chest pain days after MI may be pericarditis; weeks later may be Dresslerโ€™s syndrome.

    Categories