
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
Stroke
Current UK guidance: Acute stroke — essential diagnostic and antithrombotic principles
- Identify and exclude hypoglycaemia promptly. Send suspected acute stroke urgently to a specialist stroke pathway with brain imaging to distinguish haemorrhage from ischaemia.
- Reperfusion options (intravenous thrombolysis and mechanical thrombectomy) require specialist assessment of onset time, imaging, vascular occlusion and contraindications; do not delay referral while collecting routine investigations.
- For acute ischaemic stroke where brain imaging has excluded haemorrhage, give aspirin 300 mg promptly if not contraindicated. Important exception: after thrombolysis, delay antiplatelet therapy until at least 24 hours and after imaging has excluded significant haemorrhage (RCP National Clinical Guideline for Stroke, 2023).
- Arrange swallow screening before oral food, fluid or medicine and manage physiological disturbance. The teaching summary does not replace a local hyperacute-stroke protocol.
Reference: NICE NG128 (checked 2026-10-30). This is a targeted evidence-linked teaching update; the historic article below still requires full clinical reconciliation. Follow local protocols and the current BNF for prescribing.
🧠 Stroke = sudden focal neurological deficit due to vascular cause. ⚡ Always “Time is Brain”: prompt recognition, CT brain, and reperfusion therapy save neurons.
📊 Epidemiology
- 2nd leading cause of death worldwide 🌍.
- Most common cause of adult disability in the UK.
- ~85% ischaemic, ~15% haemorrhagic (intracerebral ± subarachnoid).
🧾 Risk Factors
- Modifiable: HTN (biggest), AF, diabetes, smoking 🚬, hyperlipidaemia, obesity, alcohol.
- Non-modifiable: age, male sex, family history, ethnicity (South Asian, Afro-Caribbean ↑ risk).
🧠 Causes of Stroke
Stroke = sudden onset of focal neurological deficit of vascular origin. ~85% are ischaemic and ~15% are haemorrhagic. Understanding the causes helps guide secondary prevention (antiplatelets, anticoagulation, BP control).
🟦 Causes of Ischaemic Stroke (≈85%)
- 🩸 Atherothromboembolism – Large artery disease (carotid stenosis, MCA, vertebrobasilar). – Plaque rupture → thrombosis → distal embolisation.
- ❤️ Cardioembolic – Atrial fibrillation (commonest cardiac cause). – Recent MI with mural thrombus. – Prosthetic valves, endocarditis (septic emboli). – Dilated cardiomyopathy.
- 🧪 Small vessel (Lacunar) disease – Lipohyalinosis & microatheroma in penetrating arteries (HTN, diabetes, smoking). – Leads to lacunar infarcts.
- 🧬 Other/uncommon causes – Arterial dissection (carotid/vertebral, esp. young pts, trauma, chiropractic manipulation). – Vasculitis (SLE, PAN, giant cell arteritis). – Thrombophilia (factor V Leiden, protein C/S deficiency, antiphospholipid). – Sickle cell disease. – Drugs (cocaine, amphetamines, OCP with smoking).
🟥 Causes of Haemorrhagic Stroke (≈15%)
- 📈 Hypertensive intracerebral haemorrhage – Chronic hypertension → lipohyalinosis, microaneurysms (Charcot–Bouchard) → rupture. – Common sites: basal ganglia, thalamus, pons, cerebellum.
- 🧬 Cerebral amyloid angiopathy – Deposition of β-amyloid in vessel walls (elderly). – Lobar haemorrhages, often recurrent.
- 💥 Aneurysm rupture – Berry aneurysm (esp. anterior communicating artery). – Causes subarachnoid haemorrhage (SAH).
- 🩸 Vascular malformations – Arteriovenous malformations (AVMs). – Cavernous haemangiomas.
- 💊 Anticoagulation / bleeding disorders – Warfarin, DOACs, thrombocytopenia, haemophilia, liver disease.
- 🧠 Neoplastic / metastatic haemorrhage – Melanoma, renal cell carcinoma, choriocarcinoma (highly vascular tumours).
- 🚬 Illicit drugs – Cocaine, amphetamines → severe HTN & vasospasm → ICH/SAH.
📊 Exam Tip
- Ischaemic = “plumbing blocked” 🚫🩸 (atherosclerosis, emboli, small vessels, dissection, clotting).
- Haemorrhagic = “pipe bursts” 💥🩸 (HTN, amyloid, aneurysm, anticoagulants, AVM, tumour).
- Always mention AF, carotid stenosis, hypertension - top 3 culprits in OSCEs.
📌 Oxford (Bamford) Stroke Classification
| Type | Criteria | Vascular territory | Prognosis |
|---|---|---|---|
| 🧠 TACS
(Total Anterior Circulation Stroke) |
All 3 of:
|
ICA or proximal MCA/ACA | Worst prognosis ⚠️ – high mortality, major disability |
| 🧠 PACS
(Partial Anterior Circulation Stroke) |
2 of the 3 TACS features OR isolated higher cortical dysfunction OR isolated hemianopia | Distal MCA or ACA | Moderate outcome, variable disability |
| 🧠 LACS
(Lacunar Stroke) |
One of the following, with no cortical signs:
|
Small vessel disease → penetrating arteries | Best prognosis 🙂, but can recur; risk of vascular dementia |
| 🧠 POCS
(Posterior Circulation Stroke) |
Brainstem/cerebellar features:
|
Vertebrobasilar circulation | Variable – can be mild (isolated visual loss) or catastrophic (locked-in) |
💡 Exam Tip: - TACS = “all 3 features”. - PACS = “2 of 3” or isolated cortical/visual. - LACS = pure motor/sensory without cortical signs. - POCS = posterior circulation signs (cranial nerves, ataxia, vertigo).
🩺 Clinical Features
- Sudden weakness/numbness (face, arm, leg).
- Speech disturbance (dysphasia, dysarthria).
- Visual loss (hemianopia, amaurosis fugax).
- Ataxia, vertigo, diplopia (posterior circulation).
- Red flag = ↓ consciousness → consider intracerebral haemorrhage or large stroke.
🚑 Acute Assessment
- 🔎 Use FAST (Face–Arm–Speech–Time) in community.
- 🩺 ABCDE, O₂ if sats <94%, IV access, BM, ECG, BP, bloods.
- 🖥️ Urgent non-contrast CT head (<1 h of arrival): exclude bleed, guide thrombolysis.
💊 Acute Management
- Ischaemic stroke:
- IV alteplase (0.9 mg/kg, max 90 mg) if within 4.5 h, no contraindications.
- Mechanical thrombectomy if large vessel occlusion ≤6 h (≤24 h in select cases).
- Aspirin 300 mg PO/NG after CT excludes bleed; switch to long-term secondary prevention later.
- Haemorrhagic stroke:
- Stop anticoagulants, correct coagulopathy (e.g. PCC for warfarin, DOAC reversal).
- Strict BP control (aim <140 mmHg systolic).
- Neurosurgical input: evacuation if large/superficial bleed, hydrocephalus, or mass effect.
💉 Benefits of Thrombolysis (IV Alteplase / Tenecteplase)
- 🚑 Widely available & rapid: Can be given in most hospitals with a CT scanner → "door-to-needle" goal ≤ 60 minutes.
- ⏱️ Time window: Effective if started within 4.5 h of symptom onset (NICE/ESO guidelines).
- 🧠 Improves functional outcomes: ~30% more patients achieve independence at 3 months compared with no thrombolysis (NINDS, ECASS trials).
- 💡 Non-invasive: IV therapy, no need for interventional facilities.
- 🔎 Bridges to thrombectomy: “Bridging therapy” - patients eligible for thrombectomy often receive IV tPA first if within the window.
🩻 Benefits of Mechanical Thrombectomy
- 🎯 Superior for large vessel occlusion (LVO): MCA (M1/M2), ICA, basilar artery → where IV thrombolysis often fails.
- ⏱️ Wider treatment window: Up to 6 h routinely, and up to 24 h in selected patients with favourable perfusion imaging (DAWN, DEFUSE-3 trials).
- 💪 Much higher recanalisation rates: >70–80% successful reperfusion vs. ~30% with IV tPA alone.
- 🧠 Improves outcomes in severe strokes: Reduces disability, increases chance of independence, lowers mortality (absolute benefit ≈ 20–30%).
- 🌍 Can be given when thrombolysis contraindicated: e.g. anticoagulation, recent surgery, high bleed risk.
📊 Key Comparison (Finals Friendly)
| 💉 IV Thrombolysis | 🩻 Mechanical Thrombectomy | |
|---|---|---|
| Route | IV alteplase / tenecteplase | Endovascular catheter retrieval |
| Time window | 0–4.5 h (selected up to 6 h) | 0–6 h; up to 24 h if favourable imaging |
| Best for | Smaller artery occlusion; early presenters | Large vessel occlusion (ICA, MCA, basilar) |
| Limitations | Risk of intracranial haemorrhage; contraindications | Needs specialist centre, interventional radiology |
| Benefit | ↑ chance of independence at 90 days (NNT ≈ 8–10) | Major reduction in disability for LVO; NNT ≈ 3–4 |
📝 Exam Tip
- Always say: Thrombolysis = first-line if within 4.5 h and no contraindications.
- Thrombectomy = for LVO up to 6 h (24 h in select cases), often after thrombolysis (“bridging”).
- Both dramatically improve functional outcome → aim is disability reduction, not just survival.
🧩 Secondary Prevention
- 🩸 Antiplatelet: clopidogrel 75 mg OD (lifelong) or aspirin + dipyridamole if not tolerated.
- 💊 Statin: atorvastatin 80 mg (if non-haemorrhagic).
- 💊 Anticoagulation: if AF confirmed, start DOAC after 3–14 days (depending on stroke size).
- ⚖️ BP target: <140/90 mmHg, ACEi/diuretic first-line.
- Lifestyle: smoking cessation 🚭, exercise, diet.
🛠️ Stroke Mimics
- Seizures (Todd’s paresis).
- Hypoglycaemia.
- Brain tumour.
- Functional neurological disorder.
- Complex migraine aura.
⚠️ Complications
- Aspiration pneumonia, dysphagia (do swallow screen in 4 h).
- Raised ICP → herniation.
- DVT/PE (immobility) → give prophylaxis (stockings + LMWH if safe).
- Depression, cognitive impairment.
- Epilepsy (post-stroke seizures).
📚 Key Exam Pearls
- “Time is Brain” ⏱️ – CT within 1 h, thrombolysis ≤4.5 h, thrombectomy ≤6 h.
- Lacunar stroke = no cortical signs.
- Thrombolysis contraindications: recent surgery, bleed, very high BP >185/110.
- Always screen swallow before giving oral meds/food 🍵.
- Secondary prevention = clopidogrel + statin + BP control.
🔗 References
🧠 Case 1 - Large-Artery Atherosclerosis
A 72-year-old man with hypertension, hyperlipidaemia, and smoking history presents with sudden left-sided weakness and dysarthria. CT head excludes haemorrhage, and carotid Doppler reveals >80% stenosis of the right internal carotid artery. 💡 Large-vessel atherosclerosis causes thrombotic occlusion or artery-to-artery embolism, most commonly at the carotid bifurcation. Management includes reperfusion (thrombolysis/thrombectomy if eligible), antiplatelets, statins, and carotid endarterectomy/stenting if severe symptomatic stenosis.
🧠 Case 2 - Cardioembolic Stroke
A 68-year-old woman with atrial fibrillation presents with sudden onset right hemiplegia and expressive aphasia. ECG shows irregularly irregular rhythm, and echocardiogram reveals left atrial enlargement. 💡 Atrial fibrillation predisposes to thrombus formation in the left atrial appendage, which can embolise to cerebral arteries, causing large territorial infarcts. Management focuses on reperfusion acutely and long-term anticoagulation to prevent recurrence.
🧠 Case 3 - Small Vessel (Lacunar) Stroke
A 60-year-old man with long-standing diabetes and hypertension develops sudden clumsy hand and dysarthria without cortical signs. MRI brain shows a small infarct in the internal capsule. 💡 Lacunar strokes result from lipohyalinosis and microatheroma affecting penetrating arteries, causing small deep infarcts. They typically present with pure motor or pure sensory syndromes. Secondary prevention involves tight blood pressure, diabetes, and lipid control alongside antiplatelet therapy.
🧠💥 Case 1 - Intracerebral Haemorrhage (Hypertensive)
A 66-year-old man with poorly controlled hypertension presents with sudden right-sided weakness, slurred speech, and reduced consciousness. CT brain shows a large basal ganglia haemorrhage. 💡 Chronic hypertension predisposes to rupture of deep perforating arteries, causing intraparenchymal bleeding, commonly in the basal ganglia, thalamus, or pons. Management is supportive with blood pressure control, neurosurgical review for large bleeds, and treatment of raised intracranial pressure, but prognosis is often poor.
🧠💥 Case 2 - Subarachnoid Haemorrhage (Aneurysmal)
A 54-year-old woman experiences a sudden “thunderclap” headache, vomiting, and photophobia while at work. Examination reveals neck stiffness but no focal deficits. CT brain confirms subarachnoid blood. 💡 Subarachnoid haemorrhage is most often due to rupture of a berry aneurysm at the circle of Willis. It presents dramatically with severe headache and meningism. Management includes urgent neurosurgical referral for aneurysm securing (clipping or coiling), nimodipine to prevent vasospasm, and supportive neurocritical care.
🧠💥 Case 3 - Lobar Haemorrhage (Cerebral Amyloid Angiopathy)
An 80-year-old woman with progressive memory decline develops sudden confusion, left-sided weakness, and seizure. CT head shows a lobar intracerebral haemorrhage in the parietal lobe. 💡 Cerebral amyloid angiopathy is a major cause of lobar haemorrhage in the elderly, due to amyloid deposition in cortical vessels, making them fragile. Unlike hypertensive bleeds, these are more superficial and recurrent. Management is supportive, with avoidance of anticoagulants/antiplatelets and consideration of neurosurgical evacuation in select cases.
Additional related clinical topics
Stroke Thrombolysis
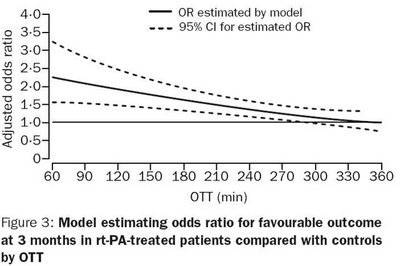
⏱️ Time is brain! Acute ischaemic stroke is a medical emergency. IV thrombolysis should be given as fast and as safely as possible in eligible patients, and mechanical thrombectomy should be pursued urgently when indicated.
🧠 Core Principle
- Exclude intracranial haemorrhage urgently with brain imaging.
- If the patient is eligible, give IV thrombolysis within 4.5 hours of symptom onset / last known well.
- Do not delay transfer for thrombectomy while waiting to see the effect of thrombolysis.
- Selected patients with wake-up stroke or presentation beyond 4.5 hours may still be eligible if advanced imaging shows salvageable brain tissue.
✅ Current Thrombolytic Drugs
- Tenecteplase is now a NICE-recommended option for acute ischaemic stroke.
- Alteplase remains an option.
- In practice, local stroke services usually use the least expensive suitable option in line with NICE guidance.
💉 Drug Protocols
- Tenecteplase
- 0.25 mg/kg IV bolus (maximum 25 mg)
- Given as a single IV bolus over about 5–10 seconds
- Much simpler logistically than alteplase
- Alteplase
- 0.9 mg/kg (maximum 90 mg)
- 10% of the total dose as an initial IV bolus
- 90% infused over 60 minutes
🧾 Who Should Be Considered for IV Thrombolysis?
- Clinical diagnosis of acute ischaemic stroke causing a disabling neurological deficit
- Intracranial haemorrhage excluded on urgent imaging
- Treatment can start within 4.5 hours of symptom onset / last known well
- Given within a well-organised stroke service with trained staff, imaging, monitoring, and re-imaging available
🕒 Extended / Imaging-Selected Thrombolysis
- Selected patients may be considered for alteplase when:
- treatment can start between 4.5 and 9 hours from known onset, or
- they have wake-up stroke and treatment can start within 9 hours of the midpoint of sleep, or
- MRI shows DWI–FLAIR mismatch suggesting salvageable tissue
- This depends on local imaging capability and stroke specialist assessment.
🚫 Major Contraindications / Reasons Not to Thrombolyse
- Intracranial haemorrhage on imaging
- Clinical suspicion of subarachnoid haemorrhage, even if CT is initially normal
- Blood pressure >185/110 mmHg despite treatment
- Current major bleeding or very high bleeding risk
- Recent major surgery / major trauma / significant invasive procedure where bleeding risk is unacceptable
- Known coagulation abnormality or anticoagulant effect that is unsafe for thrombolysis
- Very low platelets or major uncontrolled metabolic abnormality mimicking stroke
- Stroke mimic or another diagnosis judged more likely than acute ischaemic stroke
⚠️ Important Practical Points
- Age alone is not a reason to withhold thrombolysis.
- Stroke severity alone is not an absolute exclusion.
- Minor symptoms may still justify treatment if the deficit is disabling (for example aphasia, hemianopia, severe hand weakness, disabling ataxia).
- Seizure at onset is not an absolute exclusion if persistent deficits are thought to be due to stroke rather than purely post-ictal change.
- Posterior circulation stroke can be thrombolysed if otherwise eligible.
🖥️ Imaging Checklist
- Non-contrast CT head immediately if the patient may be eligible for reperfusion therapy
- If thrombectomy may be indicated, perform CT angiography after the non-contrast CT
- Add CT perfusion (or MR equivalent) if thrombectomy may be indicated beyond 6 hours or in wake-up stroke
- Large established infarction reduces the benefit and increases the risk of reperfusion therapy
- Note: A hyperdense artery sign supports large vessel occlusion and is not a contraindication to thrombolysis
🧪 Key Bedside / Lab Checks Before Thrombolysis
- Capillary blood glucose - exclude hypoglycaemia as a mimic
- Platelet count if thrombocytopenia is suspected
- Coagulation tests if anticoagulation or bleeding disorder is possible
- Weight for drug dosing
- Blood pressure
- NIHSS and pre-stroke modified Rankin score
🫀 Blood Pressure Management
- Before thrombolysis: reduce BP to <185/110 mmHg if otherwise eligible
- Monitor closely during and after treatment
- Persistent severe hypertension after treatment increases the risk of haemorrhagic transformation
🧲 Mechanical Thrombectomy
- Offer thrombectomy as soon as possible and within 6 hours for:
- acute ischaemic stroke
- proximal anterior circulation large-vessel occlusion
- usually with pre-stroke mRS <3 and NIHSS >5
- Offer thrombectomy up to 24 hours in selected patients with:
- proximal anterior circulation occlusion
- favourable advanced imaging showing salvageable tissue
- Consider thrombectomy up to 24 hours in selected posterior circulation occlusions as well.
- If eligible for thrombectomy and thrombolysis, give IV thrombolysis first unless contraindicated.
📋 First 24 Hours After IV Thrombolysis
- Close neurological and haemodynamic monitoring
- Avoid unnecessary invasive procedures if possible
- No antiplatelet or anticoagulant therapy in the first 24 hours
- Repeat brain imaging before starting antiplatelet therapy
- Start antiplatelet treatment after 24 hours once significant haemorrhage has been excluded
⚠️ Complications
- Symptomatic intracranial haemorrhage - suspect if headache, vomiting, acute hypertension, reduced consciousness, or worsening neurological deficit
- Orolingual angioedema, particularly with alteplase and especially in patients on ACE inhibitors
- Systemic bleeding
- Reperfusion injury / haemorrhagic transformation
🚨 If Deterioration Occurs During or After Thrombolysis
- Stop the infusion if alteplase is still running
- Urgent senior stroke / neurology review
- Repeat urgent brain imaging
- Manage airway, breathing, circulation, and blood pressure
- Follow local haemorrhage-reversal / complication protocols immediately
📖 Cases - Stroke Reperfusion Therapy
- Case 1 - Classic anterior circulation stroke 🧠: A 68-year-old man presents 90 minutes after onset with right hemiparesis and expressive dysphasia. CT head shows no haemorrhage. Diagnosis: acute ischaemic stroke within the standard reperfusion window. Management: IV thrombolysis plus stroke unit care.
- Case 2 - Posterior circulation stroke 🚨: A 55-year-old woman presents with sudden vertigo, vomiting, diplopia, and ataxia. CTA shows basilar artery occlusion. Management: IV thrombolysis if eligible and urgent transfer for mechanical thrombectomy.
- Case 3 - Wake-up stroke 🕒: A 72-year-old man wakes with left hemiparesis. Advanced imaging shows a small infarct core and salvageable tissue. Diagnosis: imaging-selected wake-up stroke. Management: consider reperfusion therapy according to local hyperacute stroke protocol and imaging findings.
Teaching Point 🩺:
Modern acute ischaemic stroke care is about rapid reperfusion.
Use non-contrast CT to exclude haemorrhage, add CTA when thrombectomy may be needed, and use advanced imaging for selected late-presenting or wake-up strokes.
💉 Tenecteplase is now a NICE-recommended thrombolytic option within 4.5 hours, while alteplase remains an option.
🧲 Large-vessel occlusion should trigger urgent assessment for mechanical thrombectomy.
📚 References
Stroke - General Management
🧠 Introduction
Foster Kennedy Syndrome is a rare neurological disorder defined by a striking combination of findings - optic atrophy in one eye and papilloedema in the other. It reflects both local compressive damage and raised intracranial pressure (ICP), classically from a frontal lobe or olfactory groove tumour such as a meningioma.
📚 Key Pathophysiology
- 👁️ Ipsilateral optic atrophy: Direct compression of the optic nerve by the mass leads to loss of axons and pallor of the optic disc on the same side as the lesion.
- 👁️ Contralateral papilloedema: Raised intracranial pressure causes venous congestion and swelling of the optic disc in the opposite eye, where the optic nerve is not compressed.
- 🧩 The combination is diagnostic - one disc pale (atrophic) and one swollen (oedematous).
🎯 Common Causes
- Olfactory groove meningioma - the classic cause; the tumour compresses the ipsilateral optic nerve and elevates intracranial pressure.
- Medial sphenoid wing meningioma - second most common location.
- Less commonly: frontal lobe glioma, craniopharyngioma, aneurysm, or metastatic lesion.
👀 Clinical Features
- Progressive unilateral visual loss (from optic atrophy).
- Contralateral visual blurring or headaches from raised ICP.
- Anosmia (loss of smell) if olfactory nerve compressed.
- Headache, nausea, and vomiting due to increased ICP.
- On fundoscopy:
- Atrophic disc (pale, flat) on the side of the tumour.
- Papilloedema (swollen disc margins, hyperaemia, blurred edges) on the opposite side.
🔎 Investigations
- Ophthalmic Assessment:
- Fundoscopy - confirm optic atrophy vs papilloedema pattern.
- Visual acuity and visual field testing (commonly central scotoma or field constriction).
- Imaging:
- MRI brain with contrast - gold standard for defining mass lesion and relation to optic nerves.
- CT scan - useful for identifying calcification or hyperostosis (typical in meningioma).
- ICP Assessment:
- Indirectly via clinical and imaging markers (ventricular dilation, peritumoural oedema).
- Formal ICP monitoring only if diagnosis unclear or perioperative guidance required.
- Neurological Examination: Evaluate cranial nerves I–VI, motor and sensory function, and higher cortical signs to localise lesion.
🧩 Differential Diagnosis
- Pseudo–Foster Kennedy Syndrome: Sequential optic neuritis or bilateral papilloedema with optic atrophy in one eye following chronic raised ICP (without a mass).
- Anterior ischaemic optic neuropathy or optic nerve glioma may mimic the appearance.
🩺 Management
- 🎯 Definitive Treatment – Neurosurgical:
- Surgical resection of the meningioma (often via transcranial or endoscopic approach) to relieve compression and restore CSF dynamics.
- Goal: decompress optic apparatus and reduce ICP.
- Postoperative radiotherapy may be considered for residual tumour.
- 🧴 ICP Control (Pre- and Peri-operative):
- Mannitol and dexamethasone to reduce oedema.
- Optimise positioning (head elevated 30°), maintain normocapnia and euvolaemia.
- 📅 Follow-up and Monitoring:
- Regular neuro-ophthalmologic review to monitor visual fields and disc changes.
- Postoperative MRI scans to detect recurrence or residual tumour.
- Long-term rehabilitation for persistent visual loss or olfactory deficits.
💡 Teaching Points
- Foster Kennedy Syndrome = optic atrophy + papilloedema = think frontal meningioma.
- Always exclude a mass lesion before assuming benign raised ICP (idiopathic intracranial hypertension).
- “Pseudo–Foster Kennedy” describes a similar optic appearance but without a space-occupying lesion.
- Early recognition allows curative surgery before irreversible optic damage occurs.
🧩 Summary: Foster Kennedy Syndrome is a distinct neuro-ophthalmological sign complex signalling a frontal intracranial mass. Multidisciplinary management involving neurology, neurosurgery, and ophthalmology is vital for preserving vision and preventing recurrence.
Ischaemic Stroke
| 🧾 Initial Ischaemic Stroke Management (Summary) |
|---|
|
📖 About
- Sudden onset focal neurological deficit due to reduced cerebral blood flow → infarction.
- ~80% of all strokes are ischaemic (rest haemorrhagic).
- Stroke includes brain, spinal cord, and retinal ischaemia (WHO definition).
- Diagnosis increasingly based on imaging (CT/MRI DWI) rather than just time.
🔎 Trial of Org 10172 in Acute Stroke Treatment (TOAST)
- Large-artery atherosclerosis
- Cardioembolism
- Small-vessel occlusion (lacunar)
- Other determined aetiology
- Undetermined aetiology (cryptogenic)
🧠 Causes
- Large Arterial Thrombosis: Atherosclerosis of ICA/MCA/PCA, plaque rupture, distal embolisation.
- Embolism: AF, endocarditis, LV thrombus post-MI, mitral stenosis, atrial myxoma, paradoxical embolus (PFO), aortic arch plaque, dissection.
- Small vessel disease: Lipohyalinosis → lacunar strokes (<15 mm) in internal capsule, basal ganglia, thalamus, pons.
- Venous thrombosis: Sinus thrombosis with secondary venous infarction ± haemorrhage.
- Low flow: Hypotension/shock → watershed infarcts.
- Cryptogenic: No clear cause despite work-up.
⚠️ General Risk Factors
- Hypertension, diabetes, hyperlipidaemia, smoking, age
- Arterial dissection (trauma, fibromuscular dysplasia, Marfan/Ehlers-Danlos)
- Vasculitis (GCA, PAN, Behçet’s, lupus)
- Prothrombotic states (Factor V Leiden, Protein C/S deficiency, antiphospholipid, malignancy)
- Migraine with aura, OCP/oestrogens
🩻 Investigations
- Bloods: FBC, U&E, LFT, glucose, lipids, ESR/CRP.
- ECG (AF, MI, LVH, cardiomyopathy).
- CXR (exclude cardiopulmonary causes, but don’t delay CT).
- CT Head (urgent): exclude haemorrhage. Early signs: dense MCA sign, loss of insular ribbon, grey-white loss.
- MRI DWI: more sensitive, esp. for small/early infarcts.
- Further tests (senior decision): carotid Doppler, echocardiogram, Holter (AF), vasculitis/thrombophilia screen in young.
🧾 Clinical Syndromes
- MCA: Contralateral hemiplegia (face/arm > leg), hemisensory loss, homonymous hemianopia, aphasia (dominant), neglect (non-dominant).
- ACA: Leg > arm weakness, urinary incontinence, apathy/abulia, primitive reflexes.
- Vertebrobasilar: CN palsies, contralateral weakness, sensory loss, ataxia, Horner’s syndrome.
- Lacunar: Pure motor, pure sensory, dysarthria-clumsy hand, ataxic hemiparesis.
💊 Management
- Thrombolysis: Alteplase if onset <4.5 hrs, NIHSS 4–25, CT excludes haemorrhage.
- Mechanical thrombectomy: Consider if large vessel occlusion (MCA/ICA, ≤6 hrs; up to 24 hrs in selected).
- Antiplatelet: Aspirin 300 mg OD x2 weeks then clopidogrel 75 mg OD long term. (Dual therapy not routine except in minor stroke/TIA, short course).
- Anticoagulation (AF): Start between 3–14 days depending on infarct size (TIA day 1, small stroke day 3, moderate day 6, large stroke ≥2 wks).
- BP control: Avoid acute lowering unless BP >220/120 or candidate for thrombolysis (<185/110).
- Lipids: Atorvastatin 80 mg after 48 hrs (unless contraindicated).
- Glucose: Keep 4–11 mmol/L. Avoid hypoglycaemia.
- Fluids/Nutrition: Swallow screen. NG feeding if unsafe swallow. IV fluids if nil orally.
- Oxygen: Only if sats <95%.
- VTE prophylaxis: Intermittent compression stockings. LMWH only if high-risk immobile.
- Surgery: Hemicraniectomy for malignant MCA infarct in <60 yrs.
- Carotid endarterectomy: If symptomatic carotid stenosis >70% and mild/moderate stroke.
- Rehab: Early supported discharge, MDT therapy essential.
📚 Key Classification: TOAST
- Large-artery atherosclerosis
- Cardioembolism
- Small vessel occlusion
- Other determined
- Undetermined (cryptogenic)
Mechanical Thrombectomy for Ischaemic Stroke
🧠 Mechanical thrombectomy is a life-saving endovascular procedure used to remove large clots from cerebral arteries in acute ischaemic stroke. ⚡ It has revolutionized stroke care by rapidly restoring blood flow, improving survival, and reducing long-term disability when performed promptly.
📖 About
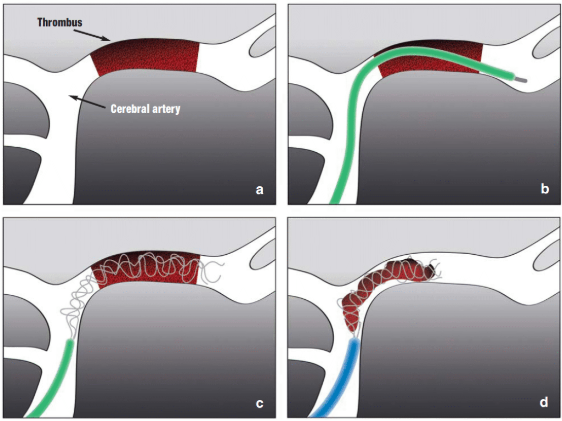
- Definition: Endovascular removal of intracranial clots in large vessel occlusion (LVO) stroke.
- History: Modern thrombectomy emerged in 2015 with stent retrievers & aspiration catheters after multiple landmark RCTs.
- Purpose: Rapid recanalization → salvage brain tissue → improve functional outcome.
📑 Evidence & Number Needed to Treat (NNT)
- Landmark RCTs:
- MR CLEAN, ESCAPE, REVASCAT, SWIFT PRIME, EXTEND-IA → all showed clear benefit over IV thrombolysis alone.
- Meta-analyses: Confirm thrombectomy is superior to medical therapy alone for LVO strokes.
- NNT:
- ~2–3 to achieve functional independence (mRS 0–2 at 90 days).
- ~6–10 to prevent one death.
- Guidelines: AHA, ESO & NICE endorse thrombectomy for eligible patients.
🧾 Pre-Thrombectomy Assessment
- Clinical: NIHSS to quantify deficit severity (higher scores suggest LVO).
- Imaging:
- NCCT: exclude haemorrhage.
- CTA: confirm large vessel occlusion.
- CTP/MR perfusion: assess penumbra vs infarct core.
- Labs: FBC, coagulation profile, renal function (contrast safety), glucose.
- Eligibility:
- Time window: ≤6h (up to 24h in selected patients by perfusion imaging).
- LVO: ICA, MCA (M1/M2), basilar artery.
- Adequate salvageable brain tissue.
- No major contraindications (extensive infarct, severe comorbidity).
🎯 Indications
- Acute ischaemic stroke with confirmed LVO.
- Within time window (6–24h depending on imaging).
- Favourable penumbra-to-core ratio on perfusion studies.
🛠️ Devices
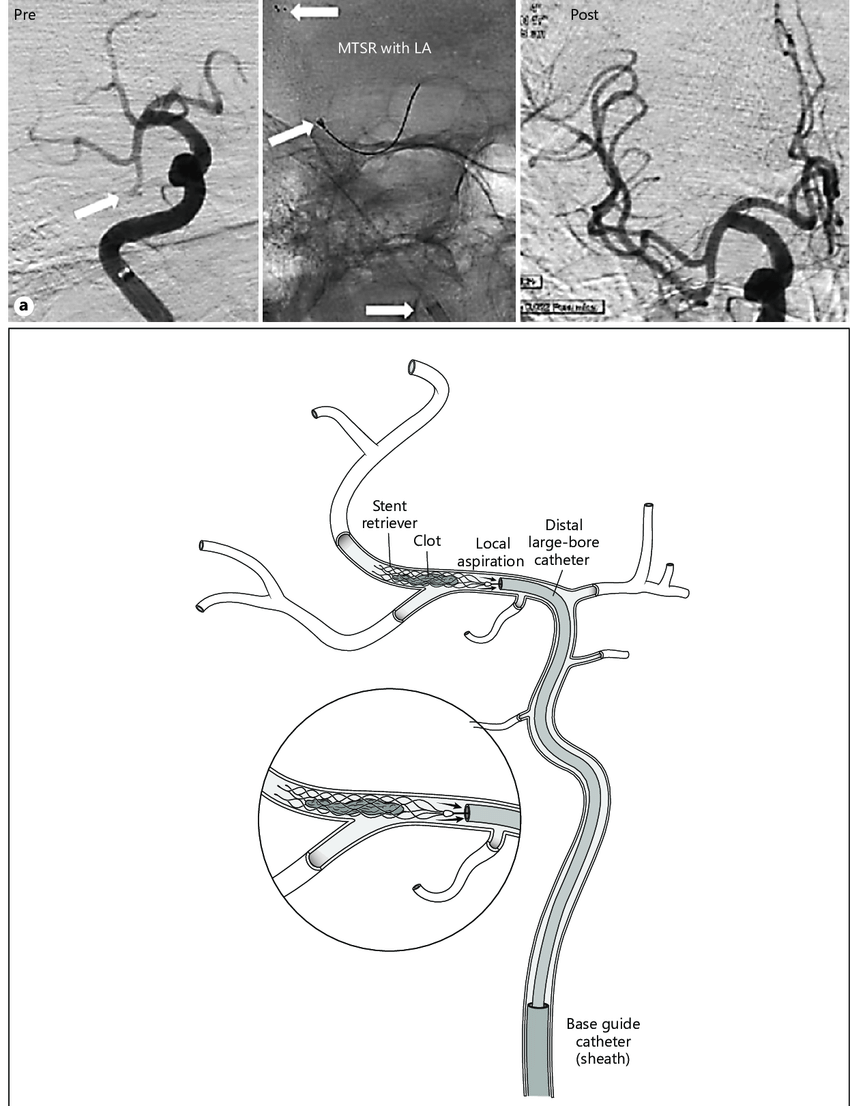
- Stent Retrievers: Solitaire, Trevo → ensnare clot & pull it out.
- Aspiration Catheters: ADAPT → suction clot out.
- Combined Techniques: Stent retriever + aspiration (Solumbra approach).
⚙️ Procedure
- Access: Usually femoral artery → navigate catheter to clot.
- Retrieval: Deploy retriever/aspiration → remove clot (multiple passes if needed).
- Verification: Angiography confirms recanalization (TICI 2b–3 = success).
- Closure: Sheath removal & haemostasis.
⚠️ Complications
- Intracranial haemorrhage (ICH).
- Vessel injury: dissection or perforation.
- Distal embolization of clot fragments.
- Access site haematoma/AV fistula.
- Reperfusion injury.
- Contrast nephropathy (rare).
📈 Outcomes
- Recanalization success in >80–90% with modern devices.
- Significant functional improvement (mRS 0–2 at 90 days in 45–60%).
- Mortality reduction compared to IV thrombolysis alone.
- “Time is brain”: benefit falls with delay.
🩺 Post-Procedure Care
- ICU/HDU monitoring for neuro status & haemodynamics.
- Follow-up CT/MRI to assess reperfusion & exclude haemorrhage.
- Early rehabilitation: physio, OT, speech therapy.
- Secondary prevention: antiplatelet/anticoagulation as indicated.
🚀 Recent Advances
- Better imaging → extended treatment windows (DAWN, DEFUSE 3 trials).
- Next-gen aspiration catheters with improved suction.
- Trials of posterior circulation thrombectomy (basilar artery occlusion).
✅ Conclusion
Mechanical thrombectomy is now gold standard therapy for eligible LVO strokes. Success depends on rapid recognition, efficient pathways, expert intervention, and careful post-stroke care. Each minute saved → better neurological recovery.
📚 References
- Goyal M, Menon BK, et al. Lancet 2016;387:1723–31.
- Albers GW, Marks MP, et al. NEJM 2018;378:708–18.
- NINDS – Mechanical Thrombectomy
- World Stroke Organization – Guidelines
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- Acute Medicine
- Anaesthetics and Critical Care
- Cardiology
- Collections
- Dermatology
- Differentials
- Drugs
- Electrocardiogram
- Emergency Medicine
- Endocrinology
- ENT
- Foundation Doctors
- Gastroenterology
- General Practice
- Genetics
- Geriatric Medicine
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Investigations
- Microbiology
- Nephrology
- Neurology
- Neurosurgery
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- OSCE
- Paediatrics
- Palliative
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Respiratory
- Resuscitation
- Revision Topics
- Rheumatology
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- Urology
- Vascular Surgery