
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
Chronic Kidney Disease (CKD)
Quick facts | emergency priorities
Clinical summary: This entry requires a disease-specific recognition, red-flag and emergency-management review. Refer to the underlying article and current local pathway; do not use this panel as a treatment protocol.
Browse the General Practice textbook: General Practice: Undifferentiated presentations, red flags and suspected cancer (specialty landing page only; no disease-level match confirmed)
References: Existing source link (not yet checked)
Editorial draft: the full historic text, doses, and pathways have not been clinically signed off. Cross-check BNF/BNFC and local protocols.
Related Subjects: |Metabolic acidosis |Lactic acidosis |Acute Kidney Injury (AKI) / Acute Renal Failure |Renal/Kidney Physiology |Chronic Kidney Disease (CKD) |Anaemia in Chronic Kidney Disease |Analgesic Nephropathy |Medullary Sponge kidney |IgA Nephropathy (Berger's disease) |HIV associated nephropathy (HIVAN) |Balkan endemic nephropathy (BEN) |Autosomal Dominant Polycystic kidney disease
📖 About (NICE-aligned)
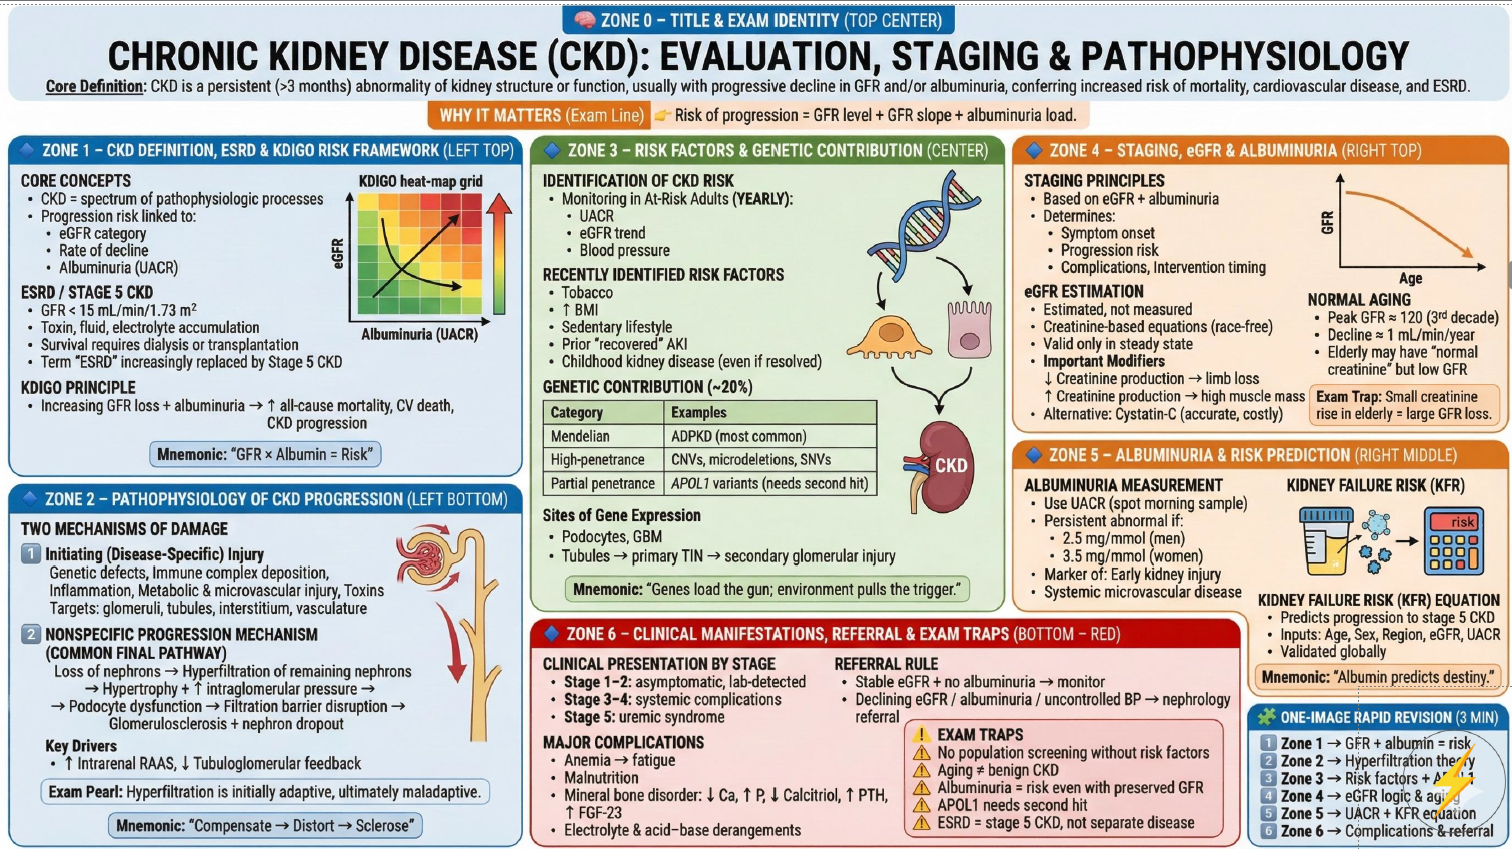
- Chronic Kidney Disease (CKD): abnormalities of kidney structure or function present for ≥3 months with implications for health.
- CKD includes: eGFR <60 mL/min/1.73m2 on ≥2 occasions ≥90 days apart (with or without markers), or markers of kidney damage (e.g. albuminuria, haematuria of renal origin, structural disease) even if eGFR is ≥60.
- Why it matters: increasing ACR and falling eGFR predict higher risk of CKD progression, AKI, and cardiovascular events.
📊 CKD Classification (use GFR + ACR)
- GFR categories (G):
- G1: ≥90 (CKD only if markers present)
- G2: 60–89 (CKD only if markers present)
- G3a: 45–59
- G3b: 30–44
- G4: 15–29
- G5: <15 (kidney failure)
- Albuminuria categories (A, by urine ACR):
- A1: <3 mg/mmol
- A2: 3–30 mg/mmol
- A3: >30 mg/mmol
🔖 Practical suffixes
- T = transplant recipient (e.g. CKD G3bA2T)
- D = dialysis (e.g. CKD G5D)
- Tip: NICE uses A1–A3 (ACR categories) rather than a “P” suffix; record the A category and the ACR value.
🧬 Aetiology (common)
- Diabetes mellitus
- Hypertension/vascular disease
- Glomerulonephritis.
- Polycystic kidney disease
- Reflux/tubulointerstitial disease
- Obstructive uropathy.
- Systemic disease (e.g. lupus, vasculitis)
- Medicines (e.g. NSAIDs, lithium)
- Myeloma (when suggested by phenotype).
🧠 Pathophysiology hook: falling eGFR reflects nephron loss; rising ACR reflects glomerular/endothelial injury. Albuminuria is a powerful “vascular damage” marker, so NICE stratifies BP targets and referral thresholds by ACR as well as GFR.
🧪 Diagnosis (NICE)
- Confirm chronicity: in a new reduced eGFR, repeat within 2 weeks to exclude AKI/acute deterioration; define progression using multiple readings over ≥90 days.
- Urine ACR: use ACR (more sensitive than PCR). If initial ACR 3–70, confirm on a repeat early-morning sample; no repeat needed if ACR ≥70.
- Urinalysis: haematuria/protein; consider renal-origin haematuria implications.
- Bloods: U&E/eGFR, potassium, bicarbonate, FBC, HbA1c (if diabetes), lipids; calcium/phosphate/PTH if advanced CKD or symptoms.
- Renal ultrasound if accelerated progression, persistent haematuria, obstruction symptoms, FHx ADPKD >20y, or eGFR <30 (G4–G5).
📉 Monitoring frequency (minimum eGFR checks per year – NICE Table 2)
- G1–G2: A1 = 0–1; A2 = 1; A3 = 1+
- G3a: A1 = 1; A2 = 1; A3 = 2
- G3b: A1 = 1–2; A2 = 2; A3 = 2+
- G4: A1 = 2; A2 = 2; A3 = 3
- G5: A1 = 4; A2 = 4+; A3 = 4+
- ACR monitoring: individualise based on risk and whether a change would alter management.
🎯 Blood pressure targets (NICE NG203)
- ACR <70 mg/mmol: aim clinic BP <140/90 (systolic target range 120–139).
- ACR ≥70 mg/mmol: aim clinic BP <130/80 (systolic target range 120–129).
- Frailty/multimorbidity: individualise (see NICE hypertension guidance).
💊 Proteinuria-lowering / kidney-protective therapy (NICE)
- Diabetes + ACR ≥3: offer ACEi or ARB titrated to the highest licensed tolerated dose.
- Hypertension + ACR >30 (A3): offer ACEi or ARB titrated to highest tolerated dose.
- No diabetes + ACR ≥70: refer and offer ACEi or ARB.
- RAAS safety: check eGFR and potassium before starting; repeat 1–2 weeks after starting and after each dose increase; avoid routine start if baseline K+ >5.0 mmol/L.
💔 CV risk reduction
- Statin: offer atorvastatin 20 mg as preferred initial high-intensity statin for people with CKD (unless contraindicated/not appropriate).
- Smoking cessation, exercise, weight and dietary salt reduction are core interventions.
- Antiplatelet therapy is for secondary prevention when indicated, balancing bleeding risk.
🩸 Anaemia of CKD (NICE)
- Investigate/manage if Hb ≤110 g/L (or symptomatic).
- Diagnostic clue: if eGFR >60, anaemia is unlikely due to CKD; if eGFR <30, CKD is often contributory but still consider other causes.
- ESA targets: do not correct to normal; typically maintain Hb 100–120 g/L in adults; avoid Hb >120 g/L (CV risk).
🦴 CKD-MBD / phosphate
- Monitor calcium/phosphate/PTH as CKD advances; manage persistent hyperphosphataemia (often in CKD 4–5) with diet and binders per local renal pathways.
🧯 Metabolic acidosis (NICE)
- Consider oral sodium bicarbonate if eGFR <30 (G4–G5) and serum bicarbonate <20 mmol/L.
🚑 When to refer (NICE NG203)
- KFRE: 5-year risk of needing RRT >5% (4-variable KFRE).
- ACR ≥70 mg/mmol (unless due to diabetes and already appropriately treated).
- ACR >30 with haematuria.
- Progression: sustained eGFR drop ≥25% with category change in 12 months, or ≥15 mL/min/1.73m2 per year.
- Resistant hypertension despite ≥4 agents, suspected genetic/rare CKD, suspected renal artery stenosis.
📚 References
- NICE NG203: Chronic kidney disease: assessment and management (Published 25 Aug 2021; last updated 24 Nov 2021)
- NICE NG203 Recommendations (BP targets, ACR confirmation, referral criteria, RAAS monitoring, anaemia, bicarbonate)
- NICE CKS: Chronic kidney disease
- NICE QS5: Statins for people with CKD (atorvastatin 20 mg)
Additional related clinical topics
Anaemia in Chronic Kidney Disease
ℹ️ About
- A very common cause of anaemia, especially in advanced CKD (stages 3–5).
- Caused mainly by reduced renal erythropoietin (EPO) production → reduced red cell synthesis.
- Contributes to fatigue, reduced exercise tolerance, left ventricular hypertrophy, and poorer quality of life.
🧬 Aetiology
- ⬇️ EPO synthesis → impaired bone marrow red cell production.
- Uraemia → shortened red cell survival.
- Iron deficiency → due to reduced absorption, chronic inflammation, and dialysis/GI blood loss.
- Folate deficiency → may occur from dialysis-related losses.
🔎 Investigations
- FBC: Normocytic, normochromic anaemia; ↓ Hb; reticulocytes low/normal.
- Blood film: Echinocytes (“burr cells”).
- U&E: Raised urea/creatinine.
- eGFR: Anaemia more likely if GFR < 30 ml/min/1.73 m².
- Iron studies: Ferritin and transferrin saturation (note: ferritin = acute-phase reactant).
- CRP/ESR: May indicate chronic inflammation.
Additional Tests (exclude other causes)
- Vitamin B12 and folate levels.
- Haemolysis screen: haptoglobin, LDH, bilirubin, DAT.
- Serum/urine protein electrophoresis ± free light chains (exclude myeloma).
- Hb electrophoresis (exclude thalassaemia/haemoglobinopathy).
- Bone marrow biopsy if cytopenias unexplained.
💊 Management
- Correct reversible causes: Replace iron, folate, or B12 as needed. ➡️ IV iron often preferred in dialysis patients.
- Erythropoiesis-stimulating agents (ESAs):
- Epoetin alfa/beta: 50–100 units/kg IV/SC, 3× weekly (often with dialysis).
- Darbepoetin alfa: Longer half-life → weekly dosing.
- Peginesatide / Methoxy-PEG-Epoetin beta: Monthly dosing.
- Target Hb: 100–120 g/L. ⚠️ Avoid overcorrection (>130 g/L) → ↑ stroke & thrombotic risk.
- Optimise CKD care: control BP, manage bone–mineral disease, ensure adequate dialysis.
References
Clinical Pearl:
Anaemia of CKD = typically normocytic + hypoproliferative.
Always exclude iron, folate, or B12 deficiency before ESAs.
Over-correcting Hb can worsen cardiovascular outcomes.
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- Acute Medicine
- Anaesthetics and Critical Care
- Anatomy
- Anatomy and Physiology
- Biochemistry
- Cardiology
- Clinical Genetics
- Clinical Immunology
- Collections
- Critical Care
- Critical care
- Dental
- Dermatology
- Differentials
- Electrocardiogram
- Embryology
- Emergency Medicine
- Endocrinology
- ENT
- Gastroenterology
- Gastroenterology & Hepatology
- General Practice
- Genetics
- Geriatric Medicine
- Guidelines
- Gynaecology
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Infographic
- Investigations
- Lists
- Microbiology
- Nephrology
- Neurology
- Neurology & Stroke
- Neurosurgery
- Obstetrics
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- OSCE
- Paediatrics
- Palliative
- Palliative Medicine
- Pathology
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Renal Medicine
- Respiratory
- Respiratory Medicine
- Resuscitation
- Revision Topics
- Rheumatology
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- Urology
- Vascular Surgery